Omnichannel Health Communication Metrics
Measuring Omnichannel Health Communication through Reach Overlap and Journey Completion
1Buckwyld Media Network, Lagos State, Nigeria
2United Bank for Africa (UBA), Nigeria
Published March 2021
Abstract
Coordinating health communication channels requires more than adding their activity counts. This conceptual analysis uses selected literature published through 2021 to develop a framework for measuring additional reach, repeated exposure, handoffs and journey completion. Campaign evaluation, implementation research and studies of digital access provide complementary perspectives, but they do not establish an independent omnichannel effect. The proposed framework distinguishes channel events from unique people and separates descriptive path attribution from causal evaluation. It specifies person or household identifiers where appropriate, event definitions, composition checks and an outcome window. A worked arithmetic example shows how channel totals overstate combined reach when audiences overlap. The paper also proposes an evaluation of coordination while holding the channel portfolio stable. Its contribution is an auditable measurement structure for assessing whether coordination changes completion of a defined health service journey. The framework is unvalidated and requires local testing of record linkage, completeness and the opportunity to use each channel.
Keywords: omnichannel communication; health communication; channel integration; measurement; attribution; health equity; campaign evaluation
1Introduction
A health communication programme might use online information, telephone contact, clinics, community organisations and entertainment content. The presence of several channels describes a portfolio. Coordination describes how a person moves between those channels without losing the information or support needed for the next step. These are different intervention features and should produce different measures [1–16].
This paper focuses on the measurement of coordination. Its unit is a person or household completing a defined service journey, with channel events recorded as intermediate observations. The framework separates additional reach, repeated exposure, channel-appropriate content and journey continuity. It treats each as a distinct claim, rather than assuming a positive result on one demonstrates the others.
Home health referral provides an application because the end of an information exchange differs from the receipt of a visit. The framework also applies to other services if the endpoint, eligibility definition and participating organisations are specified. It does not propose a universal score for all channels or a method for awarding causal credit to each recorded touchpoint [17–23].
2Research method
2.1Evaluation question and source selection
This paper addresses the following question. Does coordinating a fixed channel portfolio improve a defined journey, rather than merely increase recorded contacts?
The analysis draws on selected conceptual, measurement and empirical literature published no later than 2021. Sources are used according to their intervention, setting and outcome. Conceptual sources inform definitions and proposed relationships. Empirical studies inform the problem or an adjacent mechanism, with their findings kept within the evaluated intervention and population. The synthesis is interpretive and does not follow a registered systematic review protocol or provide an exhaustive study census [24–28].
The analytical procedure separates the target construct, the observation used to represent it and the claim supported by that observation. The resulting framework specifies process records, outcome boundaries and a prospective evaluation question. Design recommendations are identified as proposals. No participant dataset, new clinical results or validated composite score is reported, and no pooled effect is estimated from unlike interventions [7, 29–39].
The synthesis proceeds through three steps: define the communication or service task, identify the observation supported by each relevant source, and specify a comparison which would test the proposed relationship. Table 1 records construct boundaries; Table 2 operationalises a study or audit. Numerical illustrations demonstrate definitions and accounting only. They are not empirical results [40, 41].
2.2Evidence integration and applicability
Programme logic models and participatory evaluation connect activities with stated objectives and indicators [1, 42]. Behavioural intervention theory connects message design with determinants of action [43]. Campaign meta-analysis supplies evidence about evaluated campaigns, without isolating an effect attributable to channel coordination [44, 45]. Consequently, channel volume should be reported as delivery, while the proposed coordination effect requires a separate comparison [46–56].
Audience segmentation and entertainment persuasion provide reasons to adapt content to the audience and delivery context [57–59]. They do not establish a rule under which more exposures necessarily produce more action. A programme should specify which exposure is expected to inform, reinforce or support a decision and retain the corresponding outcome measures [60].
Digital access conditions affect who appears in channel records. Grossman et al [61]. review interventions to increase portal use in vulnerable populations. Okoye et al [62]. examine neighbourhood broadband and telehealth use among older adults. These sources concern digital participation, not completion of a coordinated outreach journey. Their relevance is to the opportunity to use a channel and the interpretation of comparisons between its users and nonusers [61, 64–85].
Li et al [2]. study receipt of home health after discharge referral, providing an endpoint beyond exposure. Balaban et al [87]. test patient navigation using readmission and follow-up outcomes; this is adjacent evidence rather than a channel-coordination trial. Community partnership and engagement frameworks describe participation and collaboration [88, 89]. RE-AIM, implementation outcome distinctions and implementation context frameworks support reporting reach, process and context separately [82, 86, 87, 90–119, 246, 249].
The channel portfolio should be assessed against the tasks demanded of its audience. Norman and Skinner [120] describe eHealth literacy as encompassing several skills needed to work with electronic health information. The proposed journey assessment therefore distinguishes finding information from appraising the information and completing a service request. Each step needs its own observation.
Kreps and Sparks [121] discuss health literacy needs in immigrant populations. Sheridan et al [122]. review interventions for low health literacy. These sources support attention to language and comprehension when specifying an assisted channel. Neither establishes the incremental effect of combining channels. That effect remains the subject of the proposed comparison [121–125].
Scott et al [126]. synthesize reviews of community health worker programmes. Their work provides a broader service context for a community channel, rather than a universal conversion rate. In this framework, community assistance is recorded through its assigned task and completed handoff. The evaluation should retain the specific workforce arrangement instead of treating every community contact as an interchangeable exposure [127–131].
3Results and discussion
3.1Reach overlap and journey completion framework
| Claim | Unit of analysis | Minimum measure | Main threat |
|---|---|---|---|
| Additional reach | Unique person | Deduplicated exposure across channels | Counting the same person repeatedly |
| Exposure reinforcement | Person over time | Sequence and dose of exposure | Confounding dose with motivation |
| Journey continuity | Defined handoff | Completed transitions per initiated transition | Mixing unrelated journeys |
| Equitable coverage | Eligible population stratum | Coverage and outcome by access characteristics | Excluding people unable to use digital channels |
The specification in Table 1 is analytical: its entries are proposed distinctions rather than empirical ratings or validated instrument properties.
3.1.1Four claims requiring separate comparisons
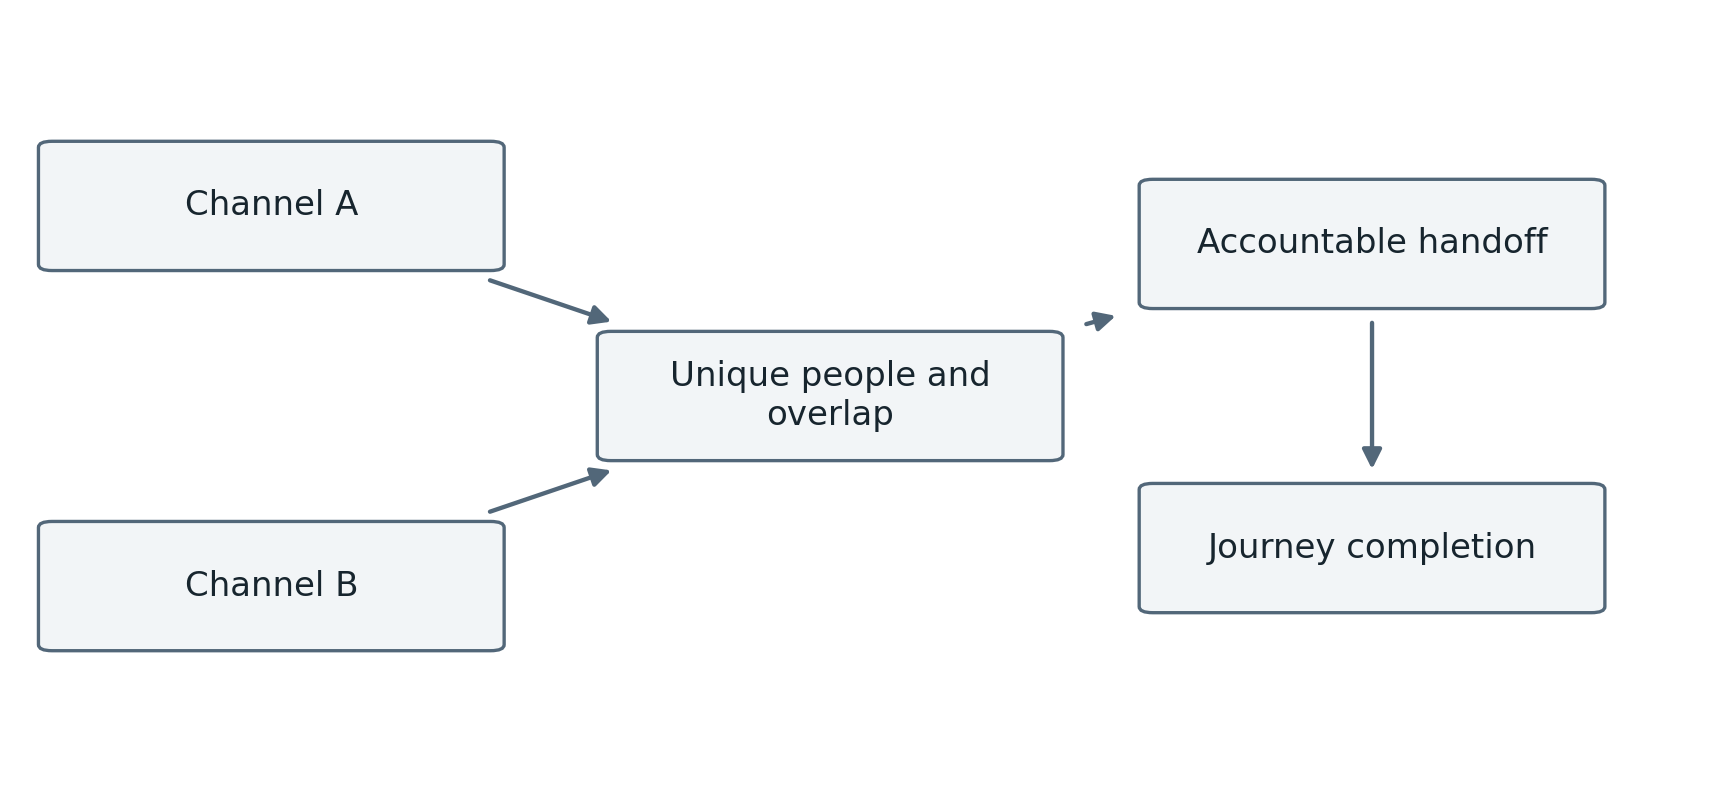
Additional reach concerns people reached by the added channel who would otherwise remain unreached. Reinforcement concerns an outcome associated with repeated exposure to specified content. Channel-appropriate messaging concerns the fit between a message, its audience and its delivery context. Journey continuity concerns whether a handoff preserves the information and support needed to complete the next step. Figure 1 places the channels within this measurement sequence; Table 1 separates the claims and their interpretation limits [132].
The intervention should state which claim is primary. Adding a channel tests a different question from assigning responsibility for a handoff within an existing portfolio. Changing the portfolio, content, eligibility process and navigator staffing simultaneously produces a package comparison. Such a comparison is useful if described accurately, but it does not reveal the independent effect of coordination [133].
3.1.2Unique reach and overlap
For two channels, combined unique reach equals reach through the first plus reach through the second minus the number reached through both. In a hypothetical example, channel A reaches 120 people, channel B reaches 100 and 70 appear in both. Combined reach is 150, while summed channel reach is 220. The extra channel reaches 30 people beyond A. These numbers illustrate arithmetic only and are not programme findings [134].
The calculation requires a defensible linkage unit. A household receiving several messages should not become several households in the denominator. Shared devices, caregiver accounts and spelling differences complicate linkage. Where identity cannot be resolved, report channel counts and the uncertainty around combined reach. Platform impressions must not be labelled unique people, and unlinked contacts must not be silently dropped.
3.1.3Journey records and outcome denominators
A proposed event record includes the linkage key, channel, event type, date, responsible organisation and evidence source. Handoff events should identify both the sending and receiving stage. A transmitted request is distinct from acknowledged receipt. For the home health application, first visit completion is distinct from a scheduled visit and from referral acceptance. Retain unresolved cases and the reasons recorded for noncompletion [117, 135–150].
Report both the proportion completing the next step among people entering that step and the proportion reaching the final endpoint among the original target cohort. The first describes a local transition; the second describes journey completion. A high final-stage conversion among selected participants does not imply broad population coverage. Present the entry population alongside the outcome so the two questions remain visible.
3.1.4Coordination evaluation and protected access routes
A prospective comparison should keep the channel portfolio and eligibility definition stable while changing the handoff process. A cluster comparison across service units is one option where contamination prevents individual assignment. The primary estimand is the effect of offering the coordinated process, not the difference between people who voluntarily used one versus several channels. Record implementation, staffing and service capacity because these conditions affect the interpretation of the contrast [151–158].
A before-and-after report is descriptive unless its design supports control of time trends and concurrent changes. Path attribution, including first-touch or last-touch credit, describes an allocation rule; it does not establish the causal contribution of a channel. Equity review should also retain a route for people reached through only one channel. A route with low volume might provide access unavailable through the rest of the portfolio [159–161].
3.1.5Distinguishing coordination from changes in composition
The main analysis should identify the cohort at the point where the coordinated process is offered. Follow the same cohort through its journey, retaining nonuse and unresolved records. People entering through later channels should not be added to an earlier cohort denominator without an explicit rule. Otherwise, a programme could appear to improve continuity by changing who counts as an entrant.
Composition should be described through characteristics relevant to opportunity and the endpoint. These might include language, access to the channels, prior service contact and the practical ability to complete the next step. Collecting a larger set of characteristics is not automatically useful. Each variable should have a stated role in describing coverage, assessing comparison balance or examining a prespecified question [162].
Coordination fidelity concerns the connection between channels. Record whether the receiving contact had the necessary information, whether the person repeated the same information and whether assistance was available at the handoff. These measures address the proposed process. They remain separate from final outcomes and from the participant's assessment of convenience. A reliable transfer might still end without service because the receiving system lacks capacity [40, 163–189].
The timing of coordination matters for interpretation. If a person has already completed the action before receiving a reminder, the reminder should not receive descriptive credit for initiating that action. If the action record has no reliable timestamp, state the temporal uncertainty. Event order does not prove causation, but an implausible order invalidates a proposed explanation. Reconcile clock conventions and reporting delays across participating systems [190–196].
The reporting unit should also preserve repeated journeys. A household might contact the programme for two different service questions, and a patient might have several referral episodes. Aggregating them as one successful person hides the unresolved episode; counting them as unrelated people overstates reach. Use separate identifiers for the person or household and the defined journey, with a documented link between them.
A cost comparison should use the same cohort and endpoint for the alternatives. Development, staffing, partner coordination and tracking are part of the coordinated process. A programme with fewer contacts might have more completed journeys; another might provide essential access to a group unreached elsewhere. Report total cost, the relevant activity or outcome denominator and the distribution of access rather than selecting the unit-cost measure producing the most favourable ranking.
3.1.6A reproducible reach and continuity analysis
Coordination is best represented as a change in the probability of progressing between specified events, conditional on entry into a defined journey. This proposal differs from increasing the number of channels or the frequency of contact. A pathway should identify the next event for which coordination is responsible, such as an acknowledged request after an information enquiry. Implementation outcome distinctions and the RE-AIM framework support separating delivery and population reach from the endpoint [90, 91, 197].
Table 2 extends the two-channel illustration to three channels. Assume, solely for demonstration, that channels A, B and C reach 120, 100 and 80 people. Their pairwise overlaps are 70, 40 and 30, and 20 people appear in all three. Unique reach equals 120 + 100 + 80 - 70 - 40 - 30 + 20, or 180 people. Summing activity yields 300, an excess of 120 over unique reach. If the target population contains 300 people, population coverage is 60 percent. These values are hypothetical and demonstrate accounting rather than programme effectiveness.
| Quantity | Illustrative value | Role in calculation |
|---|---|---|
| Channel A, B and C reach | 120, 100 and 80 | Total activity equals 300 |
| Pairwise overlaps AB, AC, BC | 70, 40 and 30 | Subtract shared contacts once |
| Triple overlap ABC | 20 | Add back after pairwise subtraction |
| Unique people reached | 180 | Population coverage equals 180 divided by 300 |
| Completed journeys | 54 | Target population completion equals 18 percent |
Source: Author-developed analytical example. Numerical values, where shown, are hypothetical and do not represent study observations.
A coordination measure should then examine what happens after reach. If 90 of the 180 reached people submit an enquiry and 54 complete the defined journey, enquiry-to-completion is 60 percent, reached-to-completion is 30 percent, and target-population completion is 18 percent. All three rates use the same 54 completed journeys but answer different questions. Reporting only the first rate obscures the population absent from the enquiry stage. Reporting only the last rate obscures where assistance is lost.
A linkage audit should sample both matched and unmatched contacts. Reviewing only accepted matches finds some erroneous merges but leaves false splits and unlinked households largely unexplored. Repeated episodes should retain a journey identifier distinct from the person identifier. Where data-sharing arrangements prevent person-level linkage, the report should provide channel-specific activity and defensible bounds rather than manufacture a precise combined count. Digital access and literacy research explain why an unlinked or absent record is not evidence of low interest [62, 120, 166, 198–225, 245, 248].
The causal comparison concerns an offered coordination process. A service unit receiving the new process should remain in its assigned group even when staff fail to complete a handoff. Comparing completed multi-channel users with single-channel users conditions on behaviour after the offer and invites selection bias. Where assignment is unavailable, a controlled rollout should document baseline differences, concurrent changes and the assumptions supporting comparison. A visual improvement in a dashboard does not remove these requirements.
Two falsifiable propositions follow. A reliable handoff should reduce requests requiring repeated information without changing the underlying service facts. A clearer receiving responsibility should reduce unresolved status at the specified reporting point. Neither proposition guarantees additional visits where service capacity is fixed. Home health receipt research supplies an endpoint beyond contact, while community workforce reviews inform the assistance context [2, 126]. The framework therefore supports a process test followed by a service-outcome comparison, with cost and excluded populations reported alongside both [63, 226–234].
Health communication increasingly takes place across multiple channels, and the language used to describe this has shifted from multichannel to omnichannel to capture a greater ambition. A multichannel programme operates several channels independently, each with its own audience, content and measures. An omnichannel programme seeks to coordinate those channels so that a person encounters consistent information and can move between them without loss of context or progress. The distinction matters because coordination is far more demanding than coexistence. It requires shared content standards, linked data, agreed definitions of success and a willingness to manage channels as parts of a system rather than as separate campaigns. Where coordination is attempted but the measurement framework remains channel-specific, the programme may believe it is operating omnichannel while its data continue to describe a set of disconnected activities. The result is a familiar pattern in which activity totals rise across every channel while the programme's contribution to the intended outcome remains unmeasured and unclear.
Reach is the most widely reported communication metric and the most frequently misunderstood. Reach describes the number of people exposed to a message, but when several channels are used, the sum of their individual reach counts the same person multiple times if they encounter more than one channel. The resulting figure, sometimes called gross reach, can greatly exceed the number of distinct people the programme has actually touched. Net reach, by contrast, describes the number of unique individuals reached by any channel. The difference between the two is the overlap, and its magnitude determines whether additional channels are expanding the audience or re-contacting people already engaged. A programme with high channel diversity and high overlap may be investing substantially in repetition rather than expansion, which is not necessarily wrong but should be a deliberate choice rather than an unnoticed consequence. Measuring overlap requires either linked data across channels or statistical methods that estimate uniqueness from marginal reach figures, and the choice of method should be documented because it affects the conclusions drawn.
Journey completion introduces a second dimension that reach alone cannot capture. A programme may reach a large audience and yet move very few of them toward the action it recommends, or it may reach fewer people and move most of them successfully. Journey completion describes the proportion of the intended population that progresses through a defined sequence of steps toward a completed outcome. Defining that sequence requires the programme to state what counts as a step, where the journey begins and ends, and what evidence demonstrates completion. These choices are consequential because they determine which channels appear effective. A channel that contributes to early awareness may look unimportant if only the final step is measured, while a channel that happens to appear immediately before completion may receive credit for progress that relied on earlier stages. Specifying the journey in advance, and recording progress at each step, allows a programme to observe where people disengage rather than merely whether the overall rate is satisfactory.
Attribution is the mechanism by which contributions are assigned to channels, and it is as much a matter of policy as of technique. Where a journey passes through several touchpoints, the final channel before an action often receives credit that properly belongs to earlier stages, a tendency that rewards channels closest to conversion and disadvantages those that build awareness or trust. Alternative rules, such as giving equal credit to all touchpoints or weighting them by position or influence, distribute credit differently and can change which channels appear worth funding. There is no universally correct rule; the appropriate choice depends on the decision the measurement is meant to inform. A programme seeking to optimise a defined conversion may reasonably weight later touchpoints heavily, while a programme seeking to build durable awareness may prefer a rule that recognises the contribution of early contact. The essential requirement is that the rule be declared in advance and applied consistently, so that comparisons across programmes and periods remain meaningful and so that the results can be interpreted by those who must act on them.
Measuring omnichannel performance requires infrastructure as well as method. Linking data across channels entails collecting identifiers, matching records and resolving conflicts, all of which raise questions about privacy, consent and the permissible uses of personal data. Where linkage is incomplete, some channels contribute observed data while others contribute only estimates, and the resulting picture is partial in ways that must be reported if conclusions are to be trustworthy. Assigning a single individual to multiple exposures also requires decisions about how to treat shared devices, household use and unauthenticated access, each of which can inflate or deflate apparent reach. Programmes should document which channels are linked, which are estimated and which are excluded, and they should distinguish assigned delivery from reported consumption. They should also distinguish unique reach from repeated exposure, since repetition may reinforce a message or may simply reflect re-contact with the same engaged people. These distinctions increase the credibility of omnichannel evaluation and reduce the risk that technical limitations are hidden behind confident-sounding aggregate figures.
Equity is an unavoidable consideration in omnichannel health communication because channel mix determines who is reached. Digital channels offer scale and efficiency, but their reach is uneven, reflecting differences in connectivity, device access, digital literacy and language. Programmes that shift heavily toward digital channels may achieve impressive aggregate reach while systematically missing the populations with the greatest unmet need, a pattern that is easy to overlook when results are reported in total. Measuring reach and journey completion by population segment exposes these disparities and allows a programme to adjust its channel mix, its message design and its supporting access routes. It also allows a programme to distinguish between a channel that is genuinely more effective and one that merely serves an already-engaged population more conveniently. Combining overlap analysis with segment-level reporting makes it possible to see whether expansion is reaching new people and whether progress is occurring across the whole intended population rather than concentrated among those already well served.
Finally, omnichannel measurement should be understood as a capability that develops over time rather than a technique applied once. Data quality improves as linkable systems mature, definitions stabilise as programmes learn what they need to observe, and attribution conventions become more meaningful as results accumulate. A programme that begins with a modest set of linked measures and expands them as infrastructure allows will produce more useful evidence than one that attempts a comprehensive system immediately and abandons it when data prove incomplete. This incremental approach also allows the programme to test its assumptions about which channels contribute to which stages, and to revise its plans in light of what it learns. Since the relationship between channels and outcomes is rarely static, repeated measurement is essential; a channel that was effective at one stage of a programme's development may be less effective later, and a channel that underperformed initially may improve as its audience and content mature. Treating measurement as an ongoing practice, rather than a one-off audit, aligns omnichannel evaluation with the reality that communication systems evolve.
The shift from multichannel to omnichannel practice has been driven partly by technology and partly by recognition that audiences do not experience communication channels in isolation. A person who sees a message on social media, discusses it with a community worker and later visits a clinic is moving through a single experience even though the programme may record these as three separate contacts. Omnichannel coordination attempts to honour that experience by ensuring consistency, continuity and mutual reinforcement across channels. Achieving it requires more than a shared logo and message; it requires shared definitions of the intended journey, linked data that allow progress to be observed, and governance that allows channels to be managed together rather than by separate teams with separate objectives. Where these requirements are unmet, coordination exists in intention but not in practice, and the programme's measurement continues to describe a collection of activities rather than a pathway toward an outcome.
Reach overlap analysis begins with a simple question that has far-reaching implications: of the people the programme reached, how many were reached more than once? The answer determines whether additional channel investment is expanding the audience or reinforcing contact with people already engaged. A programme that adds a channel with essentially the same audience as its existing channels increases gross reach while leaving net reach unchanged, which may strengthen the message for those reached but does not extend the programme's coverage. A channel that reaches a different audience increases net reach and broadens coverage, which may be valuable even if it reaches fewer people per unit of cost. Neither outcome is inherently better; the point is that they are different, and a programme cannot choose between them unless it measures overlap. Estimating overlap requires either individual-level linkage across channels or statistical techniques that infer uniqueness from marginal reach figures, and the method chosen should be reported because it affects the conclusions.
Journey completion analysis complements overlap by describing progression rather than mere contact. A programme may define its journey in several ways, from awareness to enquiry, from enquiry to referral, from referral to appointment, or from awareness all the way to a completed service contact. Each definition yields a different measure of success and identifies a different set of channels as important. The programme's decision context should determine the definition; a service seeking to increase completed visits should measure progression to a visit, while a programme seeking to improve understanding should measure progress toward comprehension. Recording intermediate steps allows the programme to see where people disengage, which is more useful than a single completion rate because it localises the difficulty. A low overall completion rate may reflect a problem at any stage, and interventions differ accordingly. Measuring the stages separately turns a disappointing headline figure into a diagnostic finding.
Attribution rules deserve particular scrutiny in omnichannel settings because they determine how channels are judged and funded. The common practice of crediting the last touchpoint before an action rewards channels that appear late in the journey and disadvantages those that build awareness or trust. This bias can lead a programme to under-invest in the channels that create the conditions for action and over-invest in those that capture it. Alternative rules distribute credit differently, and the choice among them should reflect the decision the measurement is meant to inform. A programme optimising a specific conversion may reasonably favour later touchpoints, while a programme building durable engagement may prefer a rule that recognises early contributions. Whatever rule is chosen should be declared in advance and applied consistently, so that results are comparable across channels, programmes and periods. Transparency about attribution also improves accountability, because readers can see how credit was allocated and can judge whether the allocation matches their understanding of the programme.
Data linkage is the technical foundation of omnichannel measurement and the source of its most difficult constraints. Linking records across channels requires identifiers that persist across touchpoints, agreements that permit data sharing, and processes that resolve conflicts and duplicates. Privacy regulations and audience expectations limit what can be linked, and some channels, such as broadcast or anonymous digital content, cannot be linked at all. Where linkage is partial, the programme observes some channels directly and infers others, and the resulting picture is incomplete in ways that affect interpretation. The framework therefore recommends documenting which channels are linked, which are estimated and which are excluded, and reporting the limitations this imposes. Where individual-level linkage is impossible, aggregated measures of delivery and coverage can still be reported alongside participant outcomes, provided the distinction between the two is made explicit. Being honest about linkage limitations is more useful than presenting an artificially complete picture.
Channel roles should be defined explicitly in an omnichannel programme so that each channel is managed against the task it performs best. Some channels are suited to awareness, others to explanation, others to conversion, and others to support and follow-up. A programme that tries to make every channel perform every task will manage none of them well and will be unable to interpret its results. Defining roles allows the programme to set appropriate expectations for each channel, to select measures that reflect the channel's purpose, and to evaluate contribution in terms of the role rather than against a uniform standard. It also clarifies how channels relate to one another, since a support channel that resolves questions generated by an awareness channel is contributing to completion even though it may not itself generate contacts. Where roles are defined, coordination becomes a matter of managing transitions between channels rather than of managing each channel in isolation.
Frequency and repetition deserve explicit attention because they affect both reach and effect. Repeated exposure can reinforce a message and increase the likelihood of action, but it can also produce fatigue and reduce attention where content is unchanged. The optimal frequency depends on the message, the audience and the channel, and it is rarely constant across a campaign. A programme that reports gross reach without distinguishing repetition from uniqueness cannot tell whether its audience is being reached repeatedly or whether new people are being reached. Measuring the distribution of exposure, including the proportion of the audience reached once, twice or many times, gives a more informative picture than an average. Where repetition is high and unique reach is low, the programme may benefit more from broadening its channel mix than from increasing volume in existing channels, and the evidence to support that judgement comes from measuring overlap rather than from counting contacts.
Timing and sequencing affect progression through a journey, and their importance is easily overlooked when channels are planned independently. A person who receives a message at a point when they are ready to act may progress quickly, while the same message received at a different time may be set aside. Coordinating channels allows a programme to place messages where they are most likely to be useful, and to avoid the situation in which several channels deliver similar content at the same time in a way that confuses rather than reinforces. Sequencing also allows a programme to build on earlier exposure, moving from awareness through explanation to support in an order that matches how people make decisions. Where sequencing is planned, the transitions between stages become observable and can be measured, which supports the journey completion analysis described earlier. Where it is absent, progression depends on chance and the programme cannot learn what works.
Reporting practices determine whether omnichannel evidence is usable by the people who must act on it. Reports that present only favourable aggregate figures obscure the distinctions that matter and invite misplaced confidence. Reports that present overlap, progression and segment-level results transparently allow decisions to be made on the basis of what is actually known. Effective reporting states what was measured, how it was linked, which attribution rule was applied and what limitations apply. It distinguishes unique reach from repeated exposure, delivery from consumption and observed from estimated values. It also presents results by population segment where the programme intends to serve a diverse audience. These practices may make a programme appear less successful in the short term than reports that emphasise gross figures, but they produce evidence that supports better decisions and that withstands scrutiny. Over time, honest reporting builds the credibility on which sustained investment in communication depends.
Sustainability of measurement requires that the routine collection of data be built into how programmes operate rather than added as a periodic exercise. Where data collection is treated as a project that ends, the measures it produced cease to be available and the programme loses its ability to observe its own performance. Embedding measurement requires that it be resourced as part of ongoing work, that systems be maintained and that staff be supported to collect and use data. The framework recommends that measurement be designed to be sustainable at the outset, that its burden on staff be considered and that its value be demonstrated so that it justifies continued investment. Where measurement is embedded, a programme can observe change as it occurs and adjust in time to matter, which is the point of measuring in the first place.
The framework's practical contribution is to replace a single, easily inflated measure of activity with a set of measures that describe what a programme has actually achieved. Reach overlap distinguishes expansion from repetition, journey completion distinguishes contact from progress, honest attribution prevents credit from being misallocated and segment-level reporting exposes whether the programme serves its whole intended population. Together these measures support decisions that are grounded in what is known rather than in what is convenient to report.
Adopting such measures may change a programme's conclusions about itself, and it may change how resources are allocated among channels. That is the point. Measurement that never alters a decision is unlikely to be worth its cost, and measurement that alters a decision only when the result is agreeable is not measurement at all. The framework is offered as a structure for decisions that reflect the evidence a programme can genuinely gather.
3.2Discussion of coordination findings and limits
The framework places coordination at the handoff rather than treating the number of channels as the intervention. This produces a more specific evaluation question and a practical diagnostic record. An observed loss between sending and receipt invites investigation of routing, response or documentation. It does not automatically identify low patient motivation or ineffective messaging [235–241, 251–270].
Channel comparisons require information about composition and opportunity. People who use several channels differ from people who use one, and programmes might offer different routes according to need. Adjusting observed characteristics does not remove every source of selection. Reports should separate assigned interventions, received contacts and completed outcomes, rather than using the observed path as proof of a treatment effect [242, 243].
The framework is limited by record linkage, incomplete exposure observation and uncertain population denominators. It has not been tested as a measurement instrument, and the selected literature does not establish the relative cost-effectiveness of the proposed channel portfolio. A pilot should audit linkage errors, unresolved handoffs and recording burden before making a causal comparison. The objective is trustworthy journey measurement, rather than a larger dashboard of channel activity.
The framework reframes omnichannel health communication as a problem of coordination rather than accumulation. Adding channels increases activity and cost, but it does not automatically increase the proportion of the intended population that is reached. Where audiences overlap, the same people are counted repeatedly and the incremental value of each additional channel is overstated. Reach overlap analysis addresses this directly by measuring how much of the audience is reached once, twice or many times, allowing programme managers to distinguish genuine expansion from duplicated contact. Journey completion analysis addresses the complementary question of whether the people reached progress toward the intended action. Used together, the two measures give a more honest picture of performance than aggregated activity counts and expose the common situation in which heavy channel investment produces broad contact but little completion. This distinction between reach and progress is central to designing communication that supports access rather than merely generating awareness.
Attribution deserves careful treatment because it determines how channel contributions are interpreted and rewarded. Where a journey passes through several touchpoints, the final channel before an action often receives credit that properly belongs to earlier stages, while awareness-building channels appear ineffective because their contribution is invisible in completion data. The framework recommends that attribution rules be specified in advance and that they reflect the decision the programme is trying to inform. For a programme seeking to increase access, the most useful question is which combination of channels moves a person from awareness to a completed step, not which single channel deserves credit for a purchase-like transaction. Reporting channel effects without stating the attribution rule invites disputes and can misdirect investment toward activities that capture credit rather than create value. Transparent rules also allow results to be compared across programmes and periods, which is essential if omnichannel practice is to accumulate reliable evidence.
The framework has practical implications for how equity is monitored. A programme can achieve strong aggregate reach while systematically missing the populations that most need its services, particularly where digital channels dominate and connectivity, literacy or language barriers exclude segments of the intended audience. Overlap analysis helps here as well, because it reveals whether expansion is reaching new people or re-contacting those already engaged. When reach is concentrated in already-served groups, the programme should reconsider channel mix, message design and supporting access routes rather than simply increasing volume. Measuring journey completion by population segment exposes where progress stops and why, allowing interventions to be targeted at specific transitions rather than applied uniformly. This equity lens converts omnichannel measurement from a marketing optimisation exercise into a tool for accountable service design. It also aligns communication planning with the practical obstacles audiences face when they attempt to act on health information.
Finally, the framework recognises that measurement itself requires infrastructure and discipline. Linking data across channels raises privacy and consent questions that must be resolved before analytics are built, and incomplete linkage can bias results if some channels cannot contribute data. The framework therefore recommends that programmes document which channels are linked, which are estimated and which are excluded, and that they report the limitations this imposes on conclusions. Repeated exposure should be distinguished from unique reach, and assigned delivery should be separated from reported consumption. Where individual-level linkage is not feasible, aggregated delivery statistics can still be reported alongside participant outcomes, provided the distinction is made explicit. These practices increase the credibility of omnichannel evaluation and reduce the risk that technical limitations are hidden behind confident-sounding aggregate figures. Building this measurement capability is itself an investment that improves over time as data quality and linkage methods mature.
Applying the framework in practice requires decisions about what counts as a completed journey and where the boundaries of the system lie. Programmes differ in whether completion means reaching information, requesting a service or receiving it, and the choice of endpoint determines which channels appear effective. The framework recommends that the endpoint be defined by the decision the programme is meant to inform, and that intermediate steps be recorded so that progress can be observed even where the final outcome is slow to materialise. It also recommends that the system boundary be stated explicitly, because channels outside the measured set may contribute substantially to outcomes without appearing in the data. Where a partner organisation handles part of the journey, its contribution should be included or its absence acknowledged in the reporting. Stating boundaries and endpoints in advance prevents results from being reinterpreted after the fact, and it makes comparisons across programmes more meaningful because readers know what each figure represents. As omnichannel practice matures, consistent conventions of this kind will be as important as the analytic techniques themselves in producing evidence that accumulates rather than merely accumulating reports.
The framework's value ultimately depends on whether programme teams are willing to accept that reach and progress are different things and to measure them separately. That acceptance has organisational consequences, because it may reveal that long-standing investment in a heavily used channel contributes little to completion while an unglamorous access route does most of the work. Honest measurement of this kind is uncomfortable but necessary if resources are to be directed toward the channels and supports that actually help people act on health information. The framework therefore calls for measurement practices that are transparent, comparable across programmes and explicit about their limitations, so that omnichannel communication is managed on the basis of evidence rather than on the basis of activity totals that flatter every channel equally.
4Conclusion
This paper has argued that omnichannel health communication should be evaluated through reach overlap and journey completion rather than through aggregated activity counts. Reach overlap reveals the extent to which additional channels reach new audiences or re-contact people already engaged, while journey completion shows whether those reached progress toward the intended action. Together these measures distinguish genuine expansion from duplicated contact and provide a more honest account of performance than raw channel totals. The framework additionally emphasises that attribution rules must be declared in advance so that channel contributions are interpreted consistently and investment is directed toward activities that create value rather than those that merely capture credit. It applies an equity lens by measuring reach and progress across population segments, exposing where digital-first strategies exclude the very groups they are meant to serve. Finally, it acknowledges that credible measurement depends on data linkage, consent and transparent reporting of what was observed, estimated or excluded. The framework is offered as a practical structure for accountable programme design, and its usefulness will be confirmed through application in settings where channel mix, audience diversity and access barriers can be examined together over time. Adopting shared conventions for endpoints and boundaries will determine whether omnichannel evaluation produces knowledge that accumulates across programmes.
References
- [1]Dwyer JJM, Makin S. Using a program logic model that focuses on performance measurement to develop a program. Canadian Journal of Public Health. 1997;88(6):421–425. https://doi.org/10.1007/bf03403919
- [2]Li J, Qi M, Werner RM. Assessment of receipt of the first home health care visit after hospital discharge among older adults. JAMA Network Open. 2020;3(9):e2015470. https://doi.org/10.1001/jamanetworkopen.2020.15470
- [3]Association of State and Territorial Health Officials. Community health workers: Evidence of their effectiveness. ASTHO; 2019. https://www.astho.org/globalassets/pdf/community-health-workers-summary-evidence.pdf
- [4]Feinberg IZ, Owen-Smith A, O'Connor MH, Ogrodnick MM, Rothenberg R, Eriksen MP. Strengthening culturally competent health communication. Health Security. 2021;19(S1):S-41-S-49. https://doi.org/10.1089/hs.2021.0048
- [5]Hirschman KB, Shaid E, McCauley K, Pauly MV, Naylor MD. Continuity of care: The transitional care model. Online Journal of Issues in Nursing. 2015;20(3):Manuscript 1. https://doi.org/10.3912/OJIN.Vol20No03Man01
- [6]Kaufman J, Ames H, Bosch-Capblanch X, Cartier Y, Cliff J, Glenton C, et al. The comprehensive 'communicate to vaccinate' taxonomy of communication interventions for childhood vaccination in routine and campaign contexts. BMC Public Health. 2017;17:456. https://doi.org/10.1186/s12889-017-4320-x
- [7]Aifuwa SE, Oshoba TO, Ogbuefi E, Ike PN, Nnabueze SB, Olatunde-Thorpe J. Predictive analytics models enhancing supply chain demand forecasting accuracy and reducing inventory management inefficiencies. International Journal of Multidisciplinary Research and Growth Evaluation. 2020;1(3):171–181. https://doi.org/10.54660/.IJMRGE.2020.1.3.171-181
- [8]Mistry SK, Harris E, Harris M. Community health workers as healthcare navigators in primary care chronic disease management: A systematic review. Journal of General Internal Medicine. 2021;36(9):2755–2771. https://doi.org/10.1007/s11606-021-06667-y
- [9]Nancy S, Dongre AR. Behavior change communication: Past, present, and future. Indian Journal of Community Medicine; 2021. https://pmc.ncbi.nlm.nih.gov/articles/PMC8281832/
- [10]National Collaborating Centre for Methods and Tools. Overview of health communication campaigns. NCCMT; 2019. https://www.nccmt.ca/uploads/media/media/0001/01/0a95a486b0c8bd7bccb75dc0a6c8039d5e6a92ed.pdf
- [11]Peek ME, Harmon SA, Scott SJ, Eder M, Roberson TS, Tang H, et al. Culturally tailoring patient education and communication skills training to empower African-Americans with diabetes. Translational Behavioral Medicine. 2012;2(3):296–308. https://doi.org/10.1007/s13142-012-0125-8
- [12]Shen F, Han JA. Effectiveness of entertainment education in communicating health information: A systematic review. Asian Journal of Communication. 2014;24(6):605–616. https://doi.org/10.1080/01292986.2014.927895
- [13]Shin YJ, Miller-Day M, Hecht ML, Krieger JL. Entertainment-education videos as a persuasive tool in the substance use prevention intervention 'keepin' it REAL'. Health Communication. 2018;33(7):896–906. https://doi.org/10.1080/10410236.2017.1321163
- [14]Snyder LB. Health communication campaigns and their impact on behavior. Journal of Nutrition Education and Behavior. 2007;39(2):S32–S40. https://doi.org/10.1016/j.jneb.2006.09.004
- [15]Willis N, Hill S, Kaufman J, Lewin S, Kis-Rigo J, De Castro Freire SB, et al. 'Communicate to vaccinate': The development of a taxonomy of communication interventions to improve routine childhood vaccination. BMC International Health and Human Rights. 2013;13:23. https://doi.org/10.1186/1472-698X-13-23
- [16]Zhao X. Health communication campaigns: A brief introduction and call for dialogue. International Journal of Environmental Research and Public Health. 2020;17(18):6529. https://doi.org/10.3390/ijerph17186529
- [17]Berry JG, Hall M, Dumas H, Simpser E, Whitford K, O'Neill M. Pediatric hospital discharges to home health and postacute facility care: A national study. JAMA Pediatrics. 2016;170(4):326–333. https://doi.org/10.1001/jamapediatrics.2015.4836
- [18]Davitt JK. Racial/ethnic disparities in access to Medicare home health care. Journal of Gerontological Social Work. 2010;53(7):591–610. https://doi.org/10.1080/01634372.2010.503984
- [19]National Clinical Care Commission. Report to Congress on leveraging federal programs to break the cycle of diabetes. U.S. Department of Health and Human Services; 2021.
- [20]Rennke S, Ranji SR. Transitional care strategies from hospital to home: A review for the neurohospitalist. The Neurohospitalist. 2015;5(1):35–42. https://doi.org/10.1177/1941874414540683
- [21]Schwartz ML, Kosar CM, Mroz TM, Kumar A, Rahman M. Quality of home health agencies serving traditional Medicare vs Medicare advantage beneficiaries. JAMA Network Open. 2019;2(9):e1910622. https://doi.org/10.1001/jamanetworkopen.2019.10622
- [22]Wallace AS, Luther BL, Guo JW, Wang CY, Sisler S, Fortenberry JD. Integrating social determinants of health screening and referral during routine emergency department care. BMC Public Health. 2021;21:1506. https://doi.org/10.1186/s12889-021-11527-9
- [23]Williams SC, Morton DJ, Yendro S, Rogers J. Comparing public quality ratings for accredited and nonaccredited home health agencies. Home Health Care Management & Practice. 2018;30(1):20–27. https://doi.org/10.1177/1084822317737249
- [24]Haenssgen MJ, Charoenboon N, Zanello G. Trust in healthcare: Methodological and conceptual considerations. BMJ Global Health. 2024;9(5):e014640. https://doi.org/10.1136/bmjgh-2023-014640
- [25]Lyles CR, Nguyen OK, Khoong EC, Aguilera A, Sarkar U. Multilevel determinants of digital health equity: A literature synthesis to advance the field. Annual Review of Public Health. 2023;44:383–405. https://doi.org/10.1146/annurev-publhealth-071521-023913
- [26]Mbonu IS, Aliliele C, Iwuanyanwu U, Uzoka E. A conceptual framework for risk based business intelligence architecture in financial technology platforms. International Journal of Multidisciplinary Research and Growth Evaluation. 2021;2(6):731–746. https://doi.org/10.54660/.IJMRGE.2021.2.6.731-746
- [27]Obriki OD, Arumosoye OM. Conceptual modeling of data-driven occupational safety risk control in large-scale energy infrastructure projects. Iconic Research and Engineering Journals. 2018;1(7):169–189. https://doi.org/10.64388/IREV1I7-1714414
- [28]Vanderhout S, Taneja S, Kalia K, Tang T, Wodchis WP. Uptake and user characteristics of MyChart within a Canadian community hospital with a diverse patient population: A comparative study. PLOS Digital Health. 2025;4(5):e0000852. https://doi.org/10.1371/journal.pdig.0000852
- [29]Akomolafe O, Agu MU. A review of data-driven risk evaluation models for emerging market financial institutions. Iconic Research and Engineering Journals. 2019;3(6):433–448.
- [30]American Heart Association. Mobile health interventions and remote monitoring for hypertension management. Circulation. 2022;146(Suppl_1):A12898. https://doi.org/10.1161/circ.146.suppl_1.12898
- [31]Bitomsky L, Nißen M, Kowatsch T. Equity by design principles for digital health interventions. International Journal for Equity in Health. 2025;24:112. https://doi.org/10.1186/s12939-025-02645-6
- [32]Eyetsemitan RA, Oyeleye AO, Ambali KB, Fadayomi O. Data-driven process optimization in micro-enterprises: A conceptual framework for funnel analysis and bottleneck identification. International Journal of Multidisciplinary Research and Growth Evaluation. 2024;5(6):1950–1968. https://doi.org/10.54660/IJMRGE.2024.5.6.1950-1968
- [33]Eyetsemitan RA, Ambali KB, Oyeleye AO, Fadayomi O. An integrated lean-digital framework for scaling small business operations: Synthesizing SOP design, automation, compliance, and change management. International Journal of Multidisciplinary Research and Growth Evaluation. 2025;6(6):1341–1360. https://doi.org/10.54660/IJMRGE.2025.6.6.1341-1360
- [34]Joo JY, Liu MF. Culturally tailored interventions for ethnic minorities: A scoping review. Nursing Open. 2021;8(5):2078–2090. https://doi.org/10.1002/nop2.733
- [35]Khoong EC, Lopez L, Karliner L. Addressing gaps in interpreter use: Time for implementation science informed multi-level interventions. Journal of General Internal Medicine. 2021;36(11):3532–3536. https://doi.org/10.1007/s11606-021-06823-4
- [36]Mbonu IS, Iwuanyanwu U, Aliliele C, Uzoka E. A review of VoIP forensic analytics models for financial fraud detection and regulatory compliance monitoring. International Journal of Multidisciplinary Research and Growth Evaluation. 2021;2(6):711–730. https://doi.org/10.54660/.IJMRGE.2021.2.6.711-730
- [37]Mehta B, Singh JA, Ho K, Parks M, Nelson C, Ponce B. Race, discharge disposition, and readmissions after elective hip replacement: Analysis of a large regional dataset. Health Equity. 2019;3(1):468–475. https://doi.org/10.1089/heq.2019.0083
- [38]Sanni JO, Atima ME. Analytics driven go to market frameworks addressing compliance sustainability complexity. International Journal of Multidisciplinary Research and Growth Evaluation. 2021;2(6):647–660. https://doi.org/10.54660/.ijmrge.2021.2.6.647-660
- [39]Sanni JO, Ajiga D, Atima ME. Systematic review of product management strategies in mobile network rollouts across emerging markets. International Journal of Multidisciplinary Research and Growth Evaluation. 2020;1(5):661–673. https://doi.org/10.54660/IJMRGE.2020.1.5.661-673
- [40]Agu MU, Akomolafe O, Bello A. Advances in predictive financial risk assessment using Python-based forecasting systems. International Journal of Computer Science and Mathematical Theory. 2025;11(11):131–148. https://doi.org/10.56201/ijcsmt.vol.11.no11.2025.pg131.148
- [41]Igartua JJ, Vega Casanova J. Identification with characters, elaboration, and counterarguing in entertainment-education interventions through audiovisual fiction. Journal of Health Communication. 2016;21(3):293–300. https://doi.org/10.1080/10810730.2015.1064494
- [42]Trochim WM, Marcus SE, Mâsse LC, Moser RP, Weld PC. The evaluation of large research initiatives. American Journal of Evaluation. 2008;29(1):8–28. https://doi.org/10.1177/1098214007309280
- [43]Fishbein M, Yzer MC. Using theory to design effective health behavior interventions. Communication Theory. 2003;13(2):164–183. https://doi.org/10.1111/j.1468-2885.2003.tb00287.x
- [44]Snyder LB, Hamilton MA, Mitchell EW, Kiwanuka-Tondo J, Fleming-Milici F, Proctor D. A meta-analysis of the effect of mediated health communication campaigns on behavior change in the United States. Journal of Health Communication. 2004;9(sup1):71–96. https://doi.org/10.1080/10810730490271548
- [45]Anker AE, Feeley TH, McCracken B, Lagoe CA. Measuring the effectiveness of mass-mediated health campaigns through meta-analysis. Journal of Health Communication. 2016;21(4):439–456. https://doi.org/10.1080/10810730.2015.1095820
- [46]Abbott LS, Elliott LT. Eliminating health disparities through action on the social determinants of health: A systematic review of home visiting in the United States, 2005–2015. Public Health Nursing. 2017;34(1):2–30. https://doi.org/10.1111/phn.12268
- [47]Agency for Healthcare Research and Quality. Social determinants of health and practice improvement. AHRQ; 2022. https://www.ahrq.gov/sdoh/practice-improvement.html
- [48]European Centre for Disease Prevention and Control. A literature review on health communication campaign evaluation with relevance to the prevention and control of communicable diseases. ECDC; 2020. https://www.ecdc.europa.eu/sites/default/files/media/en/publications/Publications/Campaign-evaluation.pdf
- [49]National Academies of Sciences, Engineering, and Medicine. Communities in action: Pathways to health equity. National Academies Press; 2017. https://doi.org/10.17226/24624
- [50]National Association of Chronic Disease Directors. Evaluating the effectiveness of public health communications campaigns. NACCHO; 2022. https://www.naccho.org/uploads/downloadable-resources/Webinar-2-Evaluation-Part-I.pdf
- [51]Obogo SF, Ozobu CO, Garba BMP, Adio SA. Predictive safety analytics model for early detection of high-risk construction activities. Global Journal of Engineering and Technology Review. 2026;2(3):92–109. https://doi.org/10.65150/EP-gjetr/V2E3/2026-03
- [52]Rahmani B, Montano B, Groves DW, Sharot T. The persuasive effects of narrative entertainment: A meta-analysis of recent experiments. Behavioural Public Policy, 1–30; 2025. https://doi.org/10.1017/bpp.2025.100109
- [53]Simpson A, Kelly P, Williams B. Measuring delivery and impact in community-based health programs: A four-pillar framework. BMC Public Health. 2025;25:981. https://doi.org/10.1186/s12889-025-21444-6
- [54]Updegraff JA, Rothman AJ. Message framing for health: Moderation by perceived susceptibility. In K. D. Brownell & L. M. Roberto (Eds.), Health behaviour change. Oxford University Press; 2015.
- [55]Wallerstein N, Duran B. Community-based participatory research contributions to intervention research: The intersection of Science and practice to improve health equity. American Journal of Public Health. 2010;100(S1):S40–S46. https://doi.org/10.2105/ajph.2009.184036
- [56]Wellsky C, Barnhart A. Five proven strategies to evaluate public health campaigns. KW2 Communications; 2023. https://kw2marketing.com/articles/five-proven-strategies-public-health-campaigns
- [57]Slater MD. Theory and method in health audience segmentation. Journal of Health Communication. 1996;1(3):267–284. https://doi.org/10.1080/108107396128059
- [58]Moyer-Gusé E. Toward a theory of entertainment persuasion: Explaining the persuasive effects of entertainment-education messages. Communication Theory. 2008;18(3):407–425. https://doi.org/10.1111/j.1468-2885.2008.00328.x
- [59]Brusse EDA, Fransen ML, Smit EG. Framing in entertainment-education: Effects on processes of narrative persuasion. Health Communication. 2017;32(12):1501–1509. https://doi.org/10.1080/10410236.2016.1234536
- [60]National Institute for Health and Care Excellence. Shared decision making (NICE Guideline NG197). NICE; 2021.
- [61]Grossman LV, Masterson Creber RM, Benda NC, Wright D, Vawdrey DK, Ancker JS. Interventions to increase patient portal use in vulnerable populations: A systematic review. Journal of the American Medical Informatics Association. 2019;26(8–9):855–870. https://doi.org/10.1093/jamia/ocz023
- [62]Okoye SM, Mulcahy JF, Fabius CD, Burgdorf JG, Wolff JL. Neighborhood broadband and use of telehealth among older adults: Cross-sectional study of national survey data linked with Census data. Journal of Medical Internet Research. 2021;23(6):e26242. https://doi.org/10.2196/26242
- [63]Atakpa MI. A review of predictive analytics models for anti-money laundering detection in commercial banking systems. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2021;7(2):778–804. https://doi.org/10.32628/CSEIT2064813
- [64]Armaou M, Stella A, Ramirez J. eHealth and mHealth interventions for ethnic minority and underserved populations: An umbrella review. International Journal of Community Well-Being. 2020;3(3):291–319. https://doi.org/10.1007/s42413-019-00055-5
- [65]Baim-Lance A, Angulo M, Chiasson MA, Lekas HM, Schenkel R, Villarreal J, et al. Challenges and opportunities of telehealth digital equity to manage HIV and comorbidities for older persons living with HIV in New York State. BMC Health Services Research. 2022;22(1):609. https://doi.org/10.1186/s12913-022-08010-5
- [66]Berthelsen C, Møller N, Kronborg H. Transitional care model for older adults with multiple chronic conditions: An integrative review. Journal of Clinical Nursing. 2024;33(4):1305–1320. https://doi.org/10.1111/jocn.16913
- [67]Dang S. Differences in challenges to using telehealth among older adult video and telephone users with frailty: Retrospective observational study. Journal of Medical Internet Research. https://www.jmir.org/2025/1/e69437/PDF; 2025. https://doi.org/10.2196/69437
- [68]Daniel O, Dest A, Munson A, Pulley DV, Gallo J. Interventions to enhance patient and family engagement among adults with multiple chronic conditions: A systematic scoping review. Medical Care. 2020;58(4):362–370. https://doi.org/10.1097/MLR.0000000000001286
- [69]Eruchalu CN, Pichardo MS, Bharadwaj M, Rodriguez CB, Rodriguez JA, Bergmark RW, et al. The expanding digital divide: Digital health access inequities during the COVID-19 pandemic in New York City. Journal of Urban Health. 2021;98(2):183–186. https://doi.org/10.1007/s11524-020-00508-9
- [70]Falvey JR, Sun N, Miller MJ, Pravdo A, Kodadek LM. Demystifying the digital divide: Disparities in telerehabilitation readiness among older adults in the United States. Archives of Physical Medicine and Rehabilitation. 2024;105(9):1651–1659. https://doi.org/10.1016/j.apmr.2024.05.021
- [71]Hoffman LC. Reconnecting the patient: Why telehealth policy solutions must consider the deepening digital divide. Journal of Law and Health. 2022;36(1):1–34. https://doi.org/10.18060/26409
- [72]Husain L, Greenhalgh T. Examining intersectionality and barriers to the uptake of video consultations among older adults from disadvantaged backgrounds with limited English proficiency: Qualitative narrative interview study. Journal of Medical Internet Research. 2025;27:e65690. https://doi.org/10.2196/65690
- [73]Johannes BL, Kim H, Park J. Rural-urban differences in telehealth utilization and reasons for non-use among older adults. Journal of Rural Health. 2023;39(4):733–741. https://doi.org/10.1111/jrh.12735
- [74]Leff B, Ritchie CS, Rising KL, Cannon K, Hwang U. Addressing barriers to equitable telehealth for older adults. Frontiers in Medicine. 2025;12:1483366. https://doi.org/10.3389/fmed.2025.1483366
- [75]Masterson Creber R, Dodson JA, Bidwell J, Breathett K, Lyles C, Harmon Still C, et al.; American Heart Association Cardiovascular Disease in Older Populations Committee of the Council on Clinical Cardiology and the Council on Cardiovascular and Stroke Nursing; Council on Quality of Care and Outcomes Research; Council on Peripheral Vascular Disease. Telehealth and health equity in older adults with heart failure: A scientific statement from the American Heart Association. Circulation: Cardiovascular Quality and Outcomes. 2023;16(11). https://doi.org/10.1161/hcq.0000000000000123
- [76]McCarthy MJ, Wilt K, Wilson J. Feasibility and utility of mobile health interventions for rural populations: A scoping review. JMIR mHealth and uHealth. 2024;12:e50224. https://doi.org/10.2196/50224
- [77]Miller SJ, Sly JR, Alcaraz KI, Ashing K, Baharetha H, Bhakta S, et al. Equity and behavioral digital health interventions: Strategies to improve benefit and reach. Translational Behavioral Medicine. 2023;13(6):400–405. https://doi.org/10.1093/tbm/ibad010
- [78]Nelson HD, Cantor A, Wagner J, Jungbauer R, Fu R, Stillman L, et al. Effectiveness of patient navigation to increase cancer screening in populations adversely affected by health disparities. Journal of General Internal Medicine. 2020;35(10):3026–3035. https://doi.org/10.1007/s11606-020-06020-9
- [79]Provencher V, Clemson L, Cameron JI, Richardson J, Gitlin LN. Supporting at-risk older adults transitioning from hospital to home: Who benefits from an evidence-based intervention and how? Clinical Rehabilitation. 2020;34(5):673–684. https://doi.org/10.1177/0269215520905866
- [80]University of Minnesota Rural Health Research Center. Barriers to health care access for rural Medicare beneficiaries. UMN RHRC; 2021. https://rhrc.umn.edu/wp-content/uploads/2021/01/UMN-RHC-Access-to-Care-PB_1.20.pdf
- [81]Urbanski DP, Amoako E, Bhatt A. Telehealth use among older adults receiving home health care services. JMIR Aging. 2026;9:e52147. https://doi.org/10.2196/52147
- [82]Sanders M, Sanders A, Herbert E, Booker NR, Wang S, Fiscella K. Feasibility and effectiveness of an urgent care-community partnership to reduce disparities in patient portal uptake: Quality improvement project. Journal of Participatory Medicine. 2025;17:e69253–e69253. https://doi.org/10.2196/69253
- [83]Were MC, Sinha C, Catalani C. A systematic approach to equity assessment for digital health interventions: Case example of mobile personal health records. Journal of the American Medical Informatics Association. 2019;26(8–9):884–890. https://doi.org/10.1093/jamia/ocz071
- [84]Wolff JL, Dukhanin V, Burgdorf JG, DesRoches CM. Shared access to patient portals for older adults: Implications for privacy and equity. JMIR Aging. 2022;5(2):e34628. https://doi.org/10.2196/34628
- [85]Yoon E, Hur S, Curtis LM. Disparities in patient portal use among adults with chronic conditions. JAMA Network Open. 2024;7(2):e240680. https://doi.org/10.1001/jamanetworkopen.2024.0680
- [86]Agency for Healthcare Research and Quality. Strategy 4: Care transitions from hospital to home: IDEAL discharge planning. AHRQ; 2020. https://www.ahrq.gov/patient-safety/patients-families/engagingfamilies/strategy4/index.html
- [87]Balaban RB, Galbraith AA, Burns ME, Vialle-Valentin CE, Larochelle MR, Ross-Degnan D. A patient navigator intervention to reduce hospital readmissions among high-risk safety-net patients: A randomized controlled trial. Journal of General Internal Medicine. 2015;30(7):907–915. https://doi.org/10.1007/s11606-015-3185-x
- [88]Israel BA, Schulz AJ, Parker EA, Becker AB. REVIEW OF COMMUNITY-BASED RESEARCH: Assessing partnership approaches to improve public health. Annual Review of Public Health. 1998;19(1):173–202. https://doi.org/10.1146/annurev.publhealth.19.1.173
- [89]Carman KL, Dardess P, Maurer M, Sofaer S, Adams K, Bechtel C, et al. Patient and family engagement: A framework for understanding the elements and developing interventions and policies. Health Affairs. 2013;32(2):223–231. https://doi.org/10.1377/hlthaff.2012.1133
- [90]Glasgow RE, Vogt TM, Boles SM. Evaluating the public health impact of health promotion interventions: The RE-AIM framework. American Journal of Public Health. 1999;89(9):1322–1327. https://doi.org/10.2105/ajph.89.9.1322
- [91]Proctor E, Silmere H, Raghavan R, Hovmand P, Aarons G, Bunger A, et al. Outcomes for implementation research: Conceptual distinctions, measurement challenges, and research agenda. Administration and Policy in Mental Health and Mental Health Services Research. 2011;38(2):65–76. https://doi.org/10.1007/s10488-010-0319-7
- [92]Damschroder LJ, Aron DC, Keith RE, Kirsh SR, Alexander JA, Lowery JC. Fostering implementation of health services research findings into practice: A consolidated framework for advancing implementation science. Implementation Science. 2009;4(1):50. https://doi.org/10.1186/1748-5908-4-50
- [93]Aggarwal NK, Pieh MC, Dixon L, Guarnaccia P, Alegria M, Lewis-Fernández R. Clinician descriptions of communication strategies to improve treatment engagement by racial/ethnic minorities in mental health services: A systematic review. Patient Education and Counseling. 2016;99(2):198–209. https://doi.org/10.1016/j.pec.2015.09.002
- [94]Ahn S, Romo RD, Campbell CL. A systematic review of interventions for family caregivers who care for patients with advanced cancer at home. Patient Education and Counseling. 2020;103(8):1518–1530. https://doi.org/10.1016/j.pec.2020.03.012
- [95]American Hospital Association. Building a community health worker program: The key to better care, better outcomes, and lower costs. AHA; 2018. https://www.aha.org/system/files/2018-10/chw-program-manual-2018-toolkit-final.pdf
- [96]Barello S, Castiglioni C, Bonanomi A, Graffigna G. The caregiving health engagement scale (CHE-s): Development and initial validation of a new questionnaire for measuring family caregiver engagement in healthcare. BMC Public Health. 2019;19(1):1562. https://doi.org/10.1186/s12889-019-7743-8
- [97]Basch E, Deal AM, Kris MG, Schrag D. Community health worker navigation and patient-reported outcomes. Journal of Clinical Oncology. 2023;41(31):4781–4791. https://doi.org/10.1200/JCO.23.01723
- [98]Centers for Medicare MS. Discharge planning proposed rule focuses on patient preferences. CMS; 2024. https://www.cms.gov/newsroom/press-releases/discharge-planning-proposed-rule-focuses-patient-preferences
- [99]Centers for Medicare MS. Home health quality reporting program: Measures and reporting guidance. CMS; 2024. https://www.cms.gov/medicare/quality/home-health
- [100]Cené CW, Johnson BH, Wells N, Baker B, Davis R, Turchin A. A narrative review of patient and family engagement: The 'foundation' of the medical home. Medical Care. 2016;54(7):697–717. https://doi.org/10.1097/MLR.0000000000000548
- [101]Chen AC, Fu CX, Grabowski DC. Claims-based vs agency-reported patient outcomes among home health agencies, 2013–2019. JAMA Network Open. 2024;7(4):e246813. https://doi.org/10.1001/jamanetworkopen.2024.6813
- [102]De Haes H, Bensing J. Endpoints in medical communication research, proposing a framework of functions and outcomes. Patient Education and Counseling. 2009;74(3):287–294. https://doi.org/10.1016/j.pec.2008.12.006
- [103]Dukhanin V, Topazian R, DeCamp M. Metrics and evaluation tools for patient engagement in healthcare organization- and system-level DecisionMaking: A systematic review. International Journal of Health Policy and Management. 2018;7(10):889–903. https://doi.org/10.15171/ijhpm.2018.43
- [104]Fashaw-Walters SA, Rahman M, Gee G, Mor V, White M, Thomas KS. Out of reach: Inequities in the use of high-quality home health agencies. Health Affairs. 2022;41(2):247–255. https://doi.org/10.1377/hlthaff.2021.01408
- [105]Grande GE, Austin L, Ewing G, O'Leary N, Roberts C. Assessing the impact of a carer support needs assessment tool (CSNAT) intervention in palliative home care: A stepped wedge cluster trial. BMJ Supportive & Palliative Care. 2017;7(3):326–334. https://doi.org/10.1136/bmjspcare-2014-000829
- [106]Hendren S, Griggs JJ, Epstein RM, Humiston S, Rousseau S, Jean-Pierre P, et al. Study protocol: A randomized controlled trial of patient navigation-activation to reduce cancer health disparities. BMC Cancer. 2010;10:551. https://doi.org/10.1186/1471-2407-10-551
- [107]Joynt Maddox KE, Chen LM, Zuckerman R, Epstein AM. Association between race, neighborhood, and Medicaid enrollment and outcomes in Medicare home health care. Journal of the American Geriatrics Society. 2018;66(2):239–246. https://doi.org/10.1111/jgs.15082
- [108]Keepnews D, Capitman JA. Measuring patient-level clinical outcomes of home health care. Journal of Nursing Scholarship. 2004;36(1):79–85. https://doi.org/10.1111/j.1547-5069.2004.04017.x
- [109]Kellam SG. Developing and maintaining partnerships as the foundation of implementation and implementation science: Reflections over a half century. Administration and Policy in Mental Health. 2012;39(4):317–320. https://doi.org/10.1007/s10488-011-0402-3
- [110]Kuluski K, Kokorelias KM, Peckham A. Twelve principles to support caregiver engagement in health care systems and health research. Patient Experience Journal. 2019;6(2):97–105. https://doi.org/10.35680/2372-0247.1350
- [111]Lee RM, Torres CH, Daly JG, Thomas A, Castro FG. Community partner coauthorship for increased implementation science impact: Strengthening capacity and engagement. Journal of Clinical and Translational Science. 2024;8(1):e128. https://doi.org/10.1017/cts.2024.574
- [112]Li J, Sterling MR, Kern LM. Hospital discharge planners need more information to support home health choice. Journal of the American Geriatrics Society. 2023;71(11):3512–3522. https://doi.org/10.1111/jgs.18505
- [113]McCarron TL, Noseworthy T, Moffat K, Wilkinson G, Zelinsky S, White D, et al. A co-designed framework to support and sustain patient and family engagement in health care decision making. Health Expectations. 2020;23(4):825–836. https://doi.org/10.1111/hex.13054
- [114]Patel M, Nguyen T. Insights into patient portal engagement leveraging observational electronic health data. American Journal of Managed Care. 2024;30(6):e182–e188. https://doi.org/10.37765/ajmc.2026.89870
- [115]Roland KB, Milliken EL, Rohan EA, DeGroff A, White S, Melillo S, et al. Use of community health workers and patient navigators to improve cancer outcomes among patients served by federally qualified health centers: A systematic literature review. Health Equity. 2017;1(1):61–76. https://doi.org/10.1089/heq.2017.0001
- [116]Sánchez V, Sanchez-Youngman S, Dickson E, Burgess E, Haozous E, Trickett E, et al. CBPR implementation framework for community-academic partnerships. American Journal of Community Psychology. 2021;68(1–2):3–17. https://doi.org/10.1002/ajcp.12506
- [117]Towfighi A et al. Strategies to reduce racial and ethnic inequities in stroke preparedness, care, recovery, and risk factor control. Stroke; 2023. https://www.ahajournals.org/doi/pdf/10.1161/STR.0000000000000437
- [118]Wang ML, Gallivan L, Richardson M, Bhatt A. Evaluation of a community health center patient navigation program. Preventive Medicine Reports. 2015;2:622–626. https://doi.org/10.1016/j.pmedr.2015.07.008
- [119]World Health Organization. Community engagement: A health promotion guide for universal health coverage in the hands of the people. World Health Organization; 2020. https://www.who.int/publications/i/item/9789240010529
- [120]Norman CD, Skinner HA. eHealth literacy: Essential skills for consumer health in a networked world. Journal of Medical Internet Research. 2006;8(2):e9. https://doi.org/10.2196/jmir.8.2.e9
- [121]Kreps GL, Sparks L. Meeting the health literacy needs of immigrant populations. Patient Education and Counseling. 2008;71(3):328–332. https://doi.org/10.1016/j.pec.2008.03.001
- [122]Sheridan SL, Halpern DJ, Viera AJ, Berkman ND, Donahue KE, Crotty K. Interventions for individuals with low health literacy: A systematic review. Journal of Health Communication. 2011;16(sup3):30–54. https://doi.org/10.1080/10810730.2011.604391
- [123]Agency for Healthcare Research and Quality. Health literacy universal precautions toolkit: Address language differences (Tool 9). AHRQ; 2023. https://www.ahrq.gov/health-literacy/improve/precautions/tool9.html
- [124]Center for Health Care Strategies. Screening for social determinants of health in populations with complex needs: Implementation considerations. CHCS; 2022. https://www.chcs.org/resource/screening-social-determinants-health-populations-complex-needs-implementation-considerations/
- [125]U.S. Department of Health and Human Services. Providing language services to diverse populations: Lessons from the field. CMS Office of Minority Health; 2022. https://www.cms.gov/About-CMS/Agency-Information/OMH/Downloads/Lessons-from-the-Field-508.pdf
- [126]Scott K, Beckham SW, Gross M, Pariyo G, Rao KD, Cometto G, et al. What do we know about community-based health worker programs? A systematic review of existing reviews on community health workers. Human Resources for Health. 2018;16(1):39. https://doi.org/10.1186/s12960-018-0304-x
- [127]Centers for Disease Control and Prevention. An evaluation framework for community health programs. CDC; 2019. https://stacks.cdc.gov/view/cdc/13634
- [128]Centers for Disease Control and Prevention. Evidence of impact for community health workers. Community Preventive Services Task Force; 2019. https://hdsbpc.cdc.gov/s/article/Evidence-of-Impact-for-Community-Health-Workers
- [129]Health Resources and Services Administration. Health workforce projections, 2023–2038. HRSA; 2025. https://bhw.hrsa.gov/data-research/projecting-health-workforce-supply-demand
- [130]Knowles M, Crowley AP, Vasan A, Kangovi S. Community health worker integration with and in health care and public health: A review. Annual Review of Public Health. 2023;44:363–381. https://doi.org/10.1146/annurev-publhealth-071521-031648
- [131]World Health Organization. WHO guideline on health policy and system support to optimize community health worker programmes. World Health Organization; 2020. https://www.who.int/publications/i/item/9789241550369
- [132]Quintero Johnson JM, Harrison K, Quick BL. Understanding the effectiveness of the entertainment-education strategy: An investigation of how audience involvement, message processing, and message design influence health information recall. Journal of Health Communication. 2013;18(2):160–178. https://doi.org/10.1080/10810730.2012.688244
- [133]Amadi CE, Akanbi PO, Okwah MN, Mbakwem AC, Ajuluchukwu JN. Triglyceride-glucose index and reduced kidney function in hypertensive Nigerian adults: Independent association within the cardio-renal continuum. BMC Cardiovascular Disorders. Advance online publication; 2026. https://doi.org/10.1186/s12872-026-05985-5
- [134]Ancker JS, Benda NC, Sharma MM, Johnson SB, Webber EC, Zikmund-Fisher BJ. Taxonomies for synthesizing the evidence on communicating numbers in health: Goals, format, and structure. Risk Analysis. 2022;42(12):2656–2670. https://doi.org/10.1111/risa.13875
- [135]AcademyHealth. Trust measures compendium. AcademyHealth; 2022. https://academyhealth.org/sites/default/files/publication/%5Bfield_date%3Acustom%3AY%5D-%5Bfield_date%3Acustom%3Am%5D/trust_measures_compendium.pdf
- [136]Alora Health. Mastering social determinants of health in home health. Alora Health; 2024. https://www.alorahealth.com/blog-home-health-sdoh/
- [137]Arumosoye OM, Obriki OD, Ozobu CO. Systematic review of predictive safety analytics applications in LNG projects with ESG implications. Global Journal of Engineering and Technology Review. 2026;2(2):61–73. https://doi.org/10.65150/EP-gjetr/V2E2/2026-05
- [138]Assistant Secretary for Planning and Evaluation. COVID-19 intensifies home care workforce challenges. ASPE. https://aspe.hhs.gov/reports/covid-19-intensifies-home-care-workforce-challenges; 2022. https://doi.org/10.1093/geroni/igac059.988
- [139]International Organization for Standardization. Health informatics - Requirements for a home health care record (ISO Standard No. 13606–3); 2024.
- [140]Lyles CR, Sharma AE, Fields JD, Getachew Y, Sarkar U, Zephyrin L. Centering health equity in telemedicine. The Annals of Family Medicine. 2022;20(4):362–367. https://doi.org/10.1370/afm.2823
- [141]National Institute for Health Care Management. Rural health: Addressing barriers to care. NIHCM; 2024. https://nihcm.org/publications/rural-health-addressing-barriers-to-care
- [142]O'Hara A, Paterson L. Home care workforce retention strategies: A policy brief. Home Care Association; 2024. https://hcanys.org/for-members/data-research/hca-state-of-the-industry-reports/2025-state-of-the-industry
- [143]Ogundairo KM, Ayivi-Donkor SS. Machine learning approaches to customer acquisition and retention: A framework for predictive lifecycle management. IIARD International Journal of Economics and Business Management. 2023;9(10):210–246. https://doi.org/10.56201/ijebm.v9.no10.2023.pg210.246
- [144]Okojie J, Ike P, Idu J, Nnabueze SB, Filani O, Ihwughwavwe S. Predictive analytics models for monitoring smart city emissions and infrastructure risk in urban ESG planning. International Journal of Multidisciplinary Futuristic Development. 2023;4(1):45–57. https://doi.org/10.54660/IJMFD.2023.4.1.45-57
- [145]Quigley DD, Chastain AM, Kang JA, Bronstein D, Dick AW, Stone PW, et al. Systematic review of rural and urban differences in care provided by home health agencies in the United States. Journal of the American Medical Directors Association. 2022;23(10):1653.e1–1653.e13. https://doi.org/10.1016/j.jamda.2022.08.011
- [146]Sun M, Qian Y, Liu L, Wang J, Zhuansun M, Xu T, et al. Transition of care from hospital to home for older people with chronic diseases: A qualitative study of older patients' and health care providers' perspectives. Frontiers in Public Health. 2023;11:1128885. https://doi.org/10.3389/fpubh.2023.1128885
- [147]The Medicare Advocacy Project. Racial and ethnic health care disparities in Medicare. Medicare Advocacy; 2024. https://medicareadvocacy.org/medicare-info/health-care-disparities/
- [148]University of Michigan Institute for Healthcare Policy and Innovation. Black patients less likely to get referral for home health care after hospital stay. IHPI; 2024. https://ihpi.umich.edu/news-events/news/black-patients-less-likely-get-referral-home-health-care-after-hospital-stay
- [149]Yakusheva O. Racial and ethnic disparities in home health referral among adult Medicare patients. Journal of the American Geriatrics Society. 2024;72(3):743–752. https://doi.org/10.1111/jgs.18716
- [150]Zhang S, Zhou H, Zhu Y. Have we found a solution for health misinformation? A ten-year systematic review. International Journal of Medical Informatics. 2024;187:105460. https://doi.org/10.1016/j.ijmedinf.2024.105460
- [151]Agency for Healthcare Research and Quality. AHRQ digital healthcare equity framework and implementation guide. AHRQ; 2023. https://digital.ahrq.gov/program-overview/research-stories/development-digital-healthcare-equity-framework
- [152]Merenstein Z, Shea JA, Grande D. Measuring trust in primary care. Milbank Quarterly. 2023;101(4):1187–1234. https://doi.org/10.1111/1468-0009.12666
- [153]Mitra M, Long-Bellil L, Moura I, Miles A, Kaye HS. Advancing health equity and reducing health disparities for people with disabilities in the United States. Health Affairs. 2022;41(10):1379–1386. https://doi.org/10.1377/hlthaff.2022.00499
- [154]Okonkwo CS, Agbabiaka J, Mayo W, Okeke OT. Supply chain automation framework using service management platforms. Shodhshauryam, International Scientific Refereed Research Journal. 2024;7(2):157–177. https://doi.org/10.32628/SHISRRJ2472157
- [155]Oyeleye AO, Eyetsemitan RA, Ambali KB, Fadayomi O. Reducing client onboarding cycle time in small professional services firms: A lean Six Sigma process redesign framework. Gyanshauryam, International Scientific Refereed Research Journal. 2022;5(2):467–498. https://doi.org/10.32628/GISRRJ225357
- [156]Perez LG, Merle JL, Smith JD, Dopp AR, Huebschmann AG. IM4Equity: An implementation science meta-framework for community-engaged partnerships to advance health equity. BMC Health Services Research. 2025;25(1):437. https://doi.org/10.1186/s12913-025-12537-8
- [157]Rural Health Information Hub. Social determinants of health for rural people. RHIhub; 2024. https://www.ruralhealthinfo.org/topics/social-determinants-of-health
- [158]Sanni JO. Artificial intelligence driven demand forecasting models addressing volatility in complex service organizations. Computer Science & IT Research Journal. 2026;7(1):1–26. https://doi.org/10.51594/csitrj.v7i1.2170
- [159]National Academies of Sciences, Engineering, and Medicine. The future of nursing 2020–2030: Charting a path to achieve health equity. National Academies Press; 2021. https://doi.org/10.17226/25982
- [160]The Colorado Trust. Health equity and language access: Building language access in Colorado's health system. The Colorado Trust; 2015. https://www.coloradotrust.org/wp-content/uploads/2015/03/CT_LanguageAccessBrief_final-1.pdf
- [161]Weitzman Institute. Language access and healthcare equity: Bridging the gap for limited English proficiency patients. Weitzman Institute; 2023. https://www.weitzmaninstitute.org/language-access-and-healthcare-equity-bridging-the-gap-for-limited-english-proficiency-lep-patients/
- [162]Michael ON, Ogunsola OE. Assessing the role of digital agriculture tools in shaping sustainable and inclusive food systems. Gyanshauryam, International Scientific Refereed Research Journal. 2021;4(4):154–181.
- [163]Akanbi O, Ganiu OS, Sunday EA. A multi-agent AI framework for swarm intelligence in autonomous mobile robot (AMR) fleet coordination. International Journal of Scientific Research in Humanities and Social Sciences, 2(1), 81–109. Supply Chain Management, ESG Auditing, and Sustainable Procurement; 2025.
- [164]Aliliele C, Mbonu IS, Iwuanyanwu U. A conceptual framework for continuous cloud misconfiguration monitoring and enterprise risk mitigation strategies. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(10):373–394. https://doi.org/10.32628/CSEIT2361071
- [165]Aliliele C, Mbonu IS, Iwuanyanwu U. A review of API governance and risk prioritization frameworks in modern financial institutions. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(10):395–433. https://doi.org/10.32628/CSEIT2361072
- [166]Arumosoye OM, Obriki OD. Conceptual model for emergency response readiness and capability in energy and process facilities. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(3):897–917. https://doi.org/10.32628/CSEIT25112791
- [167]Atakpa MI, Abetoh NF. A systematic review of machine learning advances in financial fraud detection for banking systems. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2022;8(2):771–801. https://doi.org/10.32628/CSEIT23906220
- [168]Dagodzo D, Ahiaeke Patrick MC. A review of right-of-way encroachment detection methods using geospatial technologies. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2022;8(1):638–667. https://doi.org/10.32628/CSEIT2281226
- [169]Dagodzo D, Ahiaeke Patrick MC. A framework for integrating drone operations into enterprise GIS systems for utility companies. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(4):924–957. https://doi.org/10.32628/CSEIT23564536
- [170]Dagodzo D, Ahiaeke Patrick MC. A review of UAV regulatory frameworks in developing economies: Progress, gaps, and recommendations. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(4):958–994. https://doi.org/10.32628/CSEIT23564537
- [171]Dagodzo D, Ahiaeke Patrick MC. A framework for national-scale UAV deployment in power infrastructure: Lessons from developing economies. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2025;11(4):779–824. https://doi.org/10.32628/CSEIT251116286
- [172]Dagodzo D, Ahiaeke Patrick MC, Aliliele C. AI and deep learning for vegetation classification in power corridor management: A review. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2022;8(1):668–698. https://doi.org/10.32628/CSEIT2281227
- [173]Eboh EE, Aliliele C. Predictive analytics systems for investment risk monitoring in SME FinTech companies and cross-border capital markets. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2025;11(2):3969–4010. https://doi.org/10.32628/CSEIT25113398
- [174]Gram EG, Nelson LM, Bhatt JR. Addressing misleading medical information on social media. BMJ Evidence-Based Medicine. 2025;30(6):420–424. https://doi.org/10.1136/bmjebm-2024-113175
- [175]Institute of Medicine. Crossing the quality chasm: A new health system for the 21st century. National Academies Press; 2001. https://doi.org/10.1136/bmj.323.7322.1192
- [176]Kaiser Family Foundation. Disparities in health measures by race and ethnicity among beneficiaries in Medicare Advantage: A review of the literature. KFF; 2024. https://www.kff.org/medicare/disparities-in-health-measures-by-race-and-ethnicity-among-beneficiaries-in-medicare-advantage-a-review-of-the-literature/
- [177]Mbonu IS, Iwuanyanwu U, Aliliele C, Uzoka E. A review of data protection impact assessment models in multi cloud financial infrastructure systems. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2022;8(1):589–623. https://doi.org/10.32628/CSEIT25442
- [178]National Committee for Quality Assurance. Building better care transitions: A practical model for outcomes, equity and coordination. NCQA; 2024. https://www.ncqa.org/videos/building-better-care-transitions-a-practical-model-for-outcomes-equity-and-coordination/
- [179]Neshan M, Padmanabhan S, Krishnan S. Screening tools to address social determinants of health in the United States: A systematic review. Journal of Clinical and Translational Science. 2024;8(1):e100. https://doi.org/10.1017/cts.2024.73
- [180]Ogbete JC, Aminu-Ibrahim AY, Iwuanyanwu OC. Integrating healing-centered design principles into diagnostic and laboratory facility planning. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2025;11(6):516–553. https://doi.org/10.32628/CSEIT251117149
- [181]Okonkwo CS, Mayo W, Okeke OT. Conceptual model for asset lifecycle management and inventory visibility. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;10(1):809–824. https://doi.org/10.32628/CSEIT2391568
- [182]Oloto AM, Yeboah TJ. Developing conceptual risk assessment models for special education documentation and accountability systems. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2025;11(4):691–734. https://doi.org/10.32628/CSEIT251116283
- [183]Osokpo OH, Travers JL, Naylor MD. Leveraging the transitional care model intervention to improve outcomes. Journal of the American Medical Directors Association. 2025;26(8):105526. https://doi.org/10.1016/j.jamda.2025.105526
- [184]Rural Health Information Hub. Telehealth and health information technology in rural healthcare. RHIhub; 2024. https://www.ruralhealthinfo.org/topics/telehealth-health-it
- [185]Sanni JO, Attah A. Market research frameworks addressing entry barriers within highly regulated industrial service sectors. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;10(2):904–930. https://doi.org/10.32628/CSEIT2342439
- [186]Seun A, Ajayi A, Elumilade RA, Bobga MA, Yeboah TJ, Ofori SD, et al. PearlAI: Hyperpersonalization and hyperlocalization as new AI affordances in basic education. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2024;10(6):2553–2568. https://doi.org/10.32628/CSEIT25113574
- [187]Seun A, Ajayi A, Yeboah TJ, Ofori SD, Elumilade RA, Apelehin AA, et al. The PearlAI framework: Leveraging artificial intelligence to transform education in Africa. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2024;10(3):1120–1132. https://doi.org/10.32628/CSEIT25113581
- [188]Westra BL, Solomon D, Ashley DM. Use of the Omaha System data to validate Medicare required outcomes in home care. Journal of Healthcare Information Management. 2006;20(4):76–84.
- [189]Yeboah TJ, Oloto AM. Conceptual models for monitoring IEP implementation fidelity and educational service delivery outcomes. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2023;9(3):944–973.
- [190]Adebayo A, Adegbite MP, Ahmed MO. Adversarial machine learning in critical infrastructure: A conceptual framework for threat modeling AI enabled OT systems. World Journal of Innovation and Modern Technology. 2022;6(1):184–234. https://doi.org/10.56201/wjimt.v6.no1.2022.pg184.234
- [191]Adebayo A, Adegbite MP, Ahmed MO. AI augmented threat detection in industrial control systems: A systematic review of machine learning approaches for ICS anomaly detection. International Journal of Engineering and Modern Technology. 2023;9(3):287–340. https://doi.org/10.56201/ijcsmt.v9.no3.2023.pg287.340
- [192]Akomolafe O, Olaogun BO, Adesuyi MO, Ndukwe VU, Sakyi JK. Smart contract automation model for supplier payment systems and performance benchmarking. International Journal of Multidisciplinary Research and Growth Evaluation. 2022;3(6):827–836. https://doi.org/10.54660/.IJMRGE.2022.3.6.827-836
- [193]Akomolafe O, Olaogun BO, Adesuyi MO, Ndukwe VU, Sakyi JK. Predictive AI model for remittance liquidity optimization in international payment systems. International Journal of Multidisciplinary Research and Growth Evaluation. 2023;4(6):1301–1311. https://doi.org/10.54660/.IJMRGE.2023.4.6.1301-1311
- [194]Aliliele C, Mbonu IS, Iwuanyanwu U. Advances in predictive analytics models for student retention and institutional risk management systems. International Journal of Advanced Multidisciplinary Research and Studies. 2023;3(6):2692–2711. https://doi.org/10.62225/2583049X.2023.3.6.5990
- [195]Borah S, Aliliele KC, Rakshit S, Vajjhala NR. Applications of artificial intelligence in software testing. In P. K. Mallick et al. (Eds.), Cognitive informatics and soft computing (Lecture Notes in Networks and Systems, Vol. 375, pp. 727–736). Springer; 2022. https://doi.org/10.1007/978-981-16-8763-1_60
- [196]Organisation for Economic Co-operation and Development. Building trustworthy 21st century healthcare systems. In Does healthcare deliver? OECD Publishing; 2025. https://doi.org/10.1787/2139da94-en
- [197]Welch V, Petkovic J, Simeon R, Presseau J, Gagnon D, Halko R, et al. Interactive social media interventions for health behaviour change, health outcomes, and health equity in the adult population. Cochrane Database of Systematic Reviews. 2018;2018(2):CD012932. https://doi.org/10.1002/14651858.CD012932.pub2
- [198]Adeyelu OO, Dagodzo D. Advances in artificial intelligence and data-driven wildlife hazard monitoring and incident reduction at international airports in west Africa. International Journal of Scientific Research in Science and Technology. 2024;11(5):872–910. https://doi.org/10.32628/IJSRST52310285
- [199]Akanbi O, Sunday EA. A systematic review of AI-driven autonomous mobile robots (AMR) in scalable micro-fulfillment centers. International Journal of Advanced Multidisciplinary Research and Studies. 2025;5(6):2363–2379. https://doi.org/10.62225/2583049X.2025.5.6.6182
- [200]Bello A, Akomolafe O, Agu MU. A conceptual framework for data-driven procurement risk management in multinational enterprises. International Journal of Advanced Multidisciplinary Research and Studies. 2023;3(6):2307–2316. https://doi.org/10.62225/2583049X.2023.3.6.5363
- [201]Boakye K, Ofori SD, Ogbona CS, Yeboah TJ, Bobga MA. Integrating ICT and mathematical thinking: Exploring the effectiveness of digital tools in secondary mathematics instruction. Iconic Research and Engineering Journals. 2020;4(4):372–398. https://doi.org/10.64388/IREV4I4-1714179
- [202]Eyetsemitan RA, Ambali KB, Oyeleye AO, Fadayomi O. Change management in small business digital transformation: A systematic review and lean change adoption framework. Gyanshauryam, International Scientific Refereed Research Journal. 2023;6(6):521–550. https://doi.org/10.32628/GISRRJ236648
- [203]Faux-Nightingale A, Philp F, Bateman J, Blagojevic-Bucknall M. Available tools to evaluate digital health literacy and engagement with eHealth resources: A scoping review. Heliyon. 2022;8(8):e10380. https://doi.org/10.1016/j.heliyon.2022.e10380
- [204]Fobellah AN. Navigating digital transformation: Auditing artificial intelligence-powered financial systems: A conceptual review. International Journal of Science and Research Archive. 2025;16(2):23–28. https://doi.org/10.30574/ijsra.2025.16.2.2274
- [205]Griffith DM, Efird CR, Baskin ML, Webb Hooper M, Davis RE, Resnicow K. Cultural sensitivity and cultural tailoring: Lessons learned and refinements after two decades of incorporating culture in health communication research. Annual Review of Public Health. 2024;45:27–43. https://doi.org/10.1146/annurev-publhealth-060722-031158
- [206]Ike PN, Okojie JS, Nnabueze SB, Idu JOO, Filani OM, Ihwughwavwe SI. Digital twin-driven environmental compliance models for sustainable procurement in oil, gas, and utilities. International Journal of Advanced Multidisciplinary Research and Studies. 2025;5(5):562–576. https://doi.org/10.62225/2583049x.2025.5.5.4960
- [207]Kaboli P, Rosenblatt RA, Ackermann RT. Health care access from the rural perspective: A narrative review. Journal of Rural Health. 2026;42(1):e70012. https://doi.org/10.1111/jrh.70012
- [208]Kbaier D, Al-Shamaileh O, Al-Hasan A. Prevalence of health misinformation on social media: Systematic review. Journal of Medical Internet Research. 2024;26:e47631. https://doi.org/10.2196/47631
- [209]Kim KK, Saggi MK, Fang Z, Ancker JS. Digital health equity frameworks and key concepts: A scoping review. Journal of the American Medical Informatics Association. 2025;32(5):855–868. https://doi.org/10.1093/jamia/ocaf024
- [210]Mbonu IS, Iwuanyanwu U, Uzoka E, Oluoha OM. Advances in enterprise log analytics and automated incident response architectures using Python and SIEM platforms. Iconic Research and Engineering Journals. 2019;3(2):1000–1019. https://doi.org/10.64388/IREV3I2-1714915
- [211]Mbonu IS, Iwuanyanwu U, Aliliele C, Uzoka E. A conceptual framework for agile supply chain digital transformation with embedded IT risk and ISO compliance controls. Iconic Research and Engineering Journals. 2020;3(11):566–593. https://doi.org/10.64388/IREV3I11-1714916
- [212]Mbonu IS, Aliliele C, Iwuanyanwu U, Uzoka E. A conceptual framework for AI enabled IT general controls and SOX audit automation processes. Gyanshauryam, International Scientific Refereed Research Journal. 2022;5(5):384–414. https://doi.org/10.32628/GISRRJ2256239
- [213]Michael ON, Ogunsola OE. Development of predictive data models for enhancing crop resilience and climate adaptation in agrarian economies. International Journal of Advanced Multidisciplinary Research and Studies. 2023;3(1):1510–1527. https://doi.org/10.62225/2583049X.2023.3.1.5143
- [214]Misra K, Keane M. Operationalizing equity: Measuring digital health access, literacy, and outcomes. HIMSS; 2024. https://www.himss.org/resources/operationalizing-equity-measuring-digital-health-access-literacy-and-outcomes/
- [215]Mukhtar T, Ahmad S, Iqbal S. Digital health literacy: A systematic review of interventions. Journal of Medical Internet Research. 2025;27:e51112. https://doi.org/10.2196/51112
- [216]Ogbete JC, Aminu-Ibrahim AY, Iwuanyanwu OC. Digital and BIM enabled coordination methods for delivering complex medical facility projects. International Journal of Advanced Multidisciplinary Research and Studies. 2025;5(6):1991–2010. https://doi.org/10.62225/2583049X.2025.5.6.5701
- [217]Okonkwo CS, Agbabiaka J, Mayo W, Okeke OT. Conceptual framework for digital supply chain governance in energy and infrastructure sectors. Gyanshauryam, International Scientific Refereed Research Journal. 2024;7(4):335–356. https://doi.org/10.32628/GISRRJ247423
- [218]Okonkwo CS, Agbabiaka J, Mayo W, Okeke OT. Model for predictive procurement planning to sustain operational uptime. International Journal of Scientific Research in Humanities and Social Sciences. 2024;1(2):909–928. https://doi.org/10.32628/IJSRSSH242772
- [219]Okonkwo CS, Agbabiaka J, Mayo W, Okeke OT. Review of digital supply chain models for cost control and operational continuity. International Journal of Advanced Multidisciplinary Research and Studies. 2024;4(6):2836–2846. https://doi.org/10.62225/2583049X.2024.4.6.5496
- [220]Olaogun BO, Adesuyi MO, Akomolafe O, Ndukwe VU, Sakyi JK. Macroeconomic impact model for blockchain-enabled payment adoption in emerging economies. International Journal of Multidisciplinary Research and Growth Evaluation. 2025;6(6):835–853. https://doi.org/10.54660/.IJMRGE.2025.6.6.835-853
- [221]Richardson S, Lawrence K, Schoenthaler AM, Mann D. A framework for digital health equity. npj Digital Medicine, 5(1), 119; 2022. https://doi.org/10.1038/s41746-022-00663-0
- [222]Rosa WE, Izumi S, Sullivan-Marx E. Community-based participatory research: A lifeline to person-centred care. Frontiers in Public Health. 2025;13:1693459. https://doi.org/10.3389/fpubh.2025.1693459
- [223]Rural Health Information Hub. Healthcare access in rural communities. RHIhub; 2024. https://www.ruralhealthinfo.org/topics/healthcare-access
- [224]Saragosa M, Nizzer S, McKay S, Kuluski K. The hospital-to-home care transition experience of home care clients: An exploratory study using patient journey mapping. BMC Health Services Research. 2023;23:830. https://doi.org/10.1186/s12913-023-09899-2
- [225]U.S. Government Accountability Office. Why health care is harder to access in rural America. GAO; 2024. https://www.gao.gov/blog/why-health-care-harder-access-rural-america
- [226]Allen J, Hutchinson AM, Brown R, Livingston PM. User experience and care integration in transitional care for older people from hospital to home: A meta-synthesis. Qualitative Health Research. 2017;27(1):24–36. https://doi.org/10.1177/1049732316658267
- [227]Center for Health Care Strategies. Community health workers offer critical supports for patients with complex health and social needs: An evidence review. CHCS; 2021. https://www.chcs.org/community-health-workers-offer-critical-supports-for-patients-with-complex-health-and-social-needs-an-evidence-review/
- [228]Dagodzo D, Ahiaeke Patrick MC. An integrated framework for UAV, LiDAR, and GIS in infrastructure corridor management. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2021;7(5):497–524. https://doi.org/10.32628/CSEIT217566
- [229]Mbonu IS, Aliliele C, Iwuanyanwu U, Uzoka E. Advances in artificial intelligence techniques for secure software testing and automated regression control mechanisms. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2021;7(5):468–496. https://doi.org/10.32628/CSEIT217565
- [230]Nápoles AM, Stewart AL. Transcreation: An implementation science framework for community-engaged behavioral interventions to reduce health disparities. BMC Health Services Research. 2018;18(1):710. https://doi.org/10.1186/s12913-018-3521-z
- [231]Penn Leonard Davis Institute. Home health care workforce is not keeping up with community needs. LDI Research Update; 2024. https://ldi.upenn.edu/our-work/research-updates/home-health-care-workforce-not-keeping-up-with-community-needs/
- [232]Perera UGE, Lim A, Lang C. The effects of home health value-based purchasing on home health care quality in for-profit and nonprofit home health agencies. Medical Care Research and Review. 2021;79(3):404–414. https://doi.org/10.1177/10775587211008690
- [233]Sunday EA, Omoegun GO, Essien MA, Oluokun OA. Transitioning from reactive to predictive maintenance in mechanical systems. International Journal of Scientific Research in Computer Science, Engineering and Information Technology. 2020;6(6):425–447. Autonomous Mobile Robotics and Warehouse Automation.
- [234]Vraga EK, Bode L. Correction as a solution for health misinformation on social media. American Journal of Public Health. 2020;110(S3):S278–S280. https://doi.org/10.2105/ajph.2020.305916
- [235]Adegbite MP, Adebayo A, Ahmed MO. An AI driven security operations architecture for utility sector SOCs: Integrating threat intelligence, behavioral analytics, and automated response. International Journal of Engineering and Modern Technology. 2024;10(11):197–256. https://doi.org/10.56201/ijemt.v10.no11.2024.pg197.256
- [236]Fischer SM, Kline DM, Min S, Okuyama-Sasaki S, Sajatovic M, Bekelman DB. Patient navigator intervention to improve palliative care outcomes. JAMA Internal Medicine. 2024;184(4):383–391. https://doi.org/10.1001/jamainternmed.2023.8220
- [237]Health Information and Management Systems Society. Improving electronic patient portal use in groups with low utilization in a family medicine practice. HIMSS; 2023. https://www.himss.org/resources/improving-electronic-patient-portal-use-groups-low-utilization-family-medicine-practice/
- [238]More KR, Phillips LA, Hartman TK. Does messaging matter? A registered report on message framing and health behaviour. Journal of Behavioral and Experimental Economics. 2024;108:102146. https://doi.org/10.1016/j.socec.2023.102146
- [239]Ogundairo KM, Ayivi-Donkor SS. Telemetry-driven value realization: Infusing economic evaluation algorithms directly into enterprise data pipelines. International Journal of Economics and Financial Management. 2023;8(8):195–232. https://doi.org/10.56201/ijefm.v8.no8.2023.pg195.232
- [240]Rural Health Information Hub. Types of evaluation in health promotion and disease prevention programs. RHIhub; 2024. https://www.ruralhealthinfo.org/toolkits/health-promotion/5/types-of-evaluation
- [241]Tuan WJ, Mellott M, Arndt BG, Jones JK, Gilchrist VJ. Disparities in use of patient portals among adults in family medicine. Journal of the American Board of Family Medicine. 2022;35(3):559–569. https://doi.org/10.3122/jabfm.2022.03.210486
- [242]Allen J, Hutchinson AM, Brown R, Livingston PM. Quality care outcomes following transitional care interventions for older people from hospital to home: A systematic review. BMC Health Services Research. 2014;14:346. https://doi.org/10.1186/1472-6963-14-346
- [243]Doré A, Rebitschek FG, Morello K, Stierstädter E, Betsch C. A systematic review and meta-analysis of the effects of entertainment-education interventions on persuasive health outcomes. Scientific Reports. 2025;15. https://doi.org/10.1038/s41598-025-11012-y
- [244]Akomolafe O, Agu MU, Bello A. A conceptual model for advancing risk governance through data-driven compliance analytics in financial institutions. Journal of Accounting and Financial Management. 2025;11(11):211–228. https://doi.org/10.56201/jafm.vol.11.no11.2025.pg211.228
- [245]Merritt MW, Williams RB. Community health worker navigation for patients with cancer: It is time to scale up. CHW Central. https://chwcentral.org/resources/community-health-worker-navigation-for-patients-with-cancer-it-is-time-to-scale-up/; 2023. https://doi.org/10.1200/jco.23.01723
- [246]Mikels JA, Taing GH, Ressler RB. The central role of affect in health message framing. Journal of Health Communication. 2020;25(10):758–766. https://doi.org/10.1080/10810730.2020.1838001
- [247]Obriki OD, Arumosoye OM. Conceptual framework for proactive hazard identification using digital safety data streams. Gyanshauryam, International Scientific Refereed Research Journal. 2023;6(3):457–481. https://doi.org/10.32628/GISRRJ236336
- [248]Van Houtven CH, Smith VA, Lindquist JH, Chapman JG, Oddone EZ, Weinberger M, et al. Family caregiver skills training to improve experiences of care: A randomized clinical trial. Journal of General Internal Medicine. 2019;34(10):2111–2118. https://doi.org/10.1007/s11606-019-05209-x
- [249]Villalobos A, Blachman-Demner D, Monje J. Community and partner engagement in dissemination and implementation research at the national institutes of health. Implementation Science Communications. 2023;4:118. https://doi.org/10.1186/s43058-023-00462-y
- [250]Wang S, Killedar A, Von Huben A, Norris S, Howell M. Evaluation of health equity frameworks in telehealth and digital health: A systematic review and narrative synthesis. Frontiers in Public Health. 2025;13:1690117. https://doi.org/10.3389/fpubh.2025.1690117
- [251]Okwesa IJ, Unamma UML, Ashore-Onisemo F, Oyesiji SO. Predictive analytics in banking: Regulatory reporting, supervision, and portfolio oversight, advances and future opportunities. Int J Res Publ Rev. 2026;7(9).
- [252]Unamma UML, Okwesa IJ, Iwuanyanwu U, Ajiga D. An offline-first design framework for digital learning in low-connectivity environments. Iconic Res Eng J. 2018;2(3):192–211. https://doi.org/10.64388/IREV2I3-1722627
- [253]Okwesa IJ, Oyesiji SO, Umar A. Digital transformation of workforce and scheduling systems. Shodhshauryam Int Sci Refereed Res J. 2023;6(6).
- [254]Ayivi-Donkor SS. Financial brand architecture optimization: Portfolio analysis and economic value. Gulf J Adv Bus Res. 2026;4(3):145–164.
- [255]Okoli I, Kinyanjui A, Mensah KO, Agboada P, Pedro O. Data-driven auditing in payroll and receivables: Predictive models for enhancing accuracy in financial statement validation. Int J Sci Res Comput Sci Eng Inf Technol. 2022;8(5):851–889. https://doi.org/10.32628/CSEIT23902204
- [256]Pedro O, Kinyanjui A, Okoli I, Mensah KO, Agboada P. Advances in digital lending profitability and financial inclusion strategies in emerging markets. Int J Sci Res Comput Sci Eng Inf Technol. 2024;10(4):1207–1243. https://doi.org/10.32628/CSEIT251116287
- [257]Okoli I, Pedro O, Kinyanjui A, Mensah KO, Agboada P. Predictive loan default analytics: Machine learning for early-warning detection and recovery optimization in commercial lending portfolios. Shodhshauryam Int Sci Refereed Res J. 2022;5(5):535–585. https://doi.org/10.32628/SHISRRJ225897
- [258]Mensah KO, Kinyanjui A, Okoli I, Agboada P, Pedro O. Advances in asset liability management and interest rate risk modeling in retail and investment banking. IRE J. 2023;6(9):583–618. https://doi.org/10.64388/IREV6I9-1723268
- [259]Mensah KO, Pedro O, Kinyanjui A, Okoli I, Agboada P. A conceptual model for integrated enterprise risk management and capital allocation in financial institutions. IRE J. 2019;3(1):684–719. https://doi.org/10.64388/IREV3I1-1723266
- [260]Mensah KO, Pedro O, Kinyanjui A, Okoli I, Agboada P. A review of capital adequacy frameworks and risk weighted asset optimization in modern banking systems. IRE J. 2019;3(6):731–768. https://doi.org/10.64388/IREV3I6-1723267
- [261]Mensah KO, Kinyanjui A, Okoli I, Agboada P, Pedro O. A conceptual model for regulatory compliance cost efficiency and sustainable financial performance. Int J Technol. 2025;1(2):329–349.
- [262]Kinyanjui A, Okoli I, Pedro O, Mensah KO, Agboada P. From audit associate to senior: A leadership-oriented study on driving reporting accuracy and efficiency gains in complex audit environments. Int J Multidiscip Res Growth Eval. 2024;5(6):2130–2149. https://doi.org/10.54660/IJMRGE.2024.5.6.2130-2149
- [263]Mensah KO, Kinyanjui A, Pedro O, Okoli I, Agboada P. Advances in AI driven credit risk modeling and predictive loan default analytics in commercial banking. Int J Multidiscip Res Growth Eval. 2022;3(6):1258–1280. https://doi.org/10.54660/IJMRGE.2022.3.6.1258-1280
- [264]Kinyanjui A, Pedro O, Okoli I, Mensah KO, Agboada P. A review of ESG integration and climate risk disclosure effects on bank valuation and financial stability. Int J Multidiscip Res Growth Eval. 2021;2(6):1244–1267. https://doi.org/10.54660/IJMRGE.2021.2.6.1244-1267
- [265]Asibor E, Ninduwezuor-Ehiobu N, Olisakwe HC. Integrating HAZOP, reliability analysis, and risk-based decision-making into critical energy infrastructure design. Int J Sci Res Comput Sci Eng Inf Technol. 2023;9(1):958–999. https://doi.org/10.32628/CSEIT2391574
- [266]Asibor E, Isong DE. Risk-based process engineering framework for strengthening reliability across complex natural gas infrastructure systems. IRE J. 2019;3(2):1020–1060. https://doi.org/10.64388/IREV3I2-1723153
- [267]Asibor E, Isong DE. Flare-gas recovery technologies for advancing energy security, environmental performance, and resource efficiency. IRE J. 2020;4(1):369–410. https://doi.org/10.64388/IREV4I1-1723154
- [268]Asibor E, Olisakwe HC. Methane emissions reduction strategies for safer and more efficient petroleum production operations. Int J Multidiscip Res Growth Eval. 2022;3(4):739–763. https://doi.org/10.54660/IJMRGE.2022.3.4.739-763
- [269]Asibor E, Olisakwe HC, Isong DE, Uwagboe FM, Amarahobu C. Techno-economic framework for converting routinely flared gas into marketable energy products and feedstocks. Int J Res Publ Rev. 2026;7(9):3255–3283. https://doi.org/10.55248/gengpi.07.0926.3004
- [270]Asibor E. Artificial intelligence applications for detecting process failures across oil and gas facilities. Int J Technol. 2025;1(2):350–373.